RCOM RADIOLOGICAL CASE OF THE MONTH
Applied Radiology — Vol. 33 , Issue 2 , pp. 37 -39
DOI: 10.37549/AR1222
Published: February 1, 2004
Categories
CASE SUMMARY
A 73-year-old white male who complained of abdominal pain underwent a contrast-enhanced computed tomography (CT) examination of the abdomen (Figure 1). This study revealed an infrarenal abdominal aortic aneurysm measuring 8 cm in greatest anteroposterior diameter. Contrast opacification of both kidneys was shown on this CT.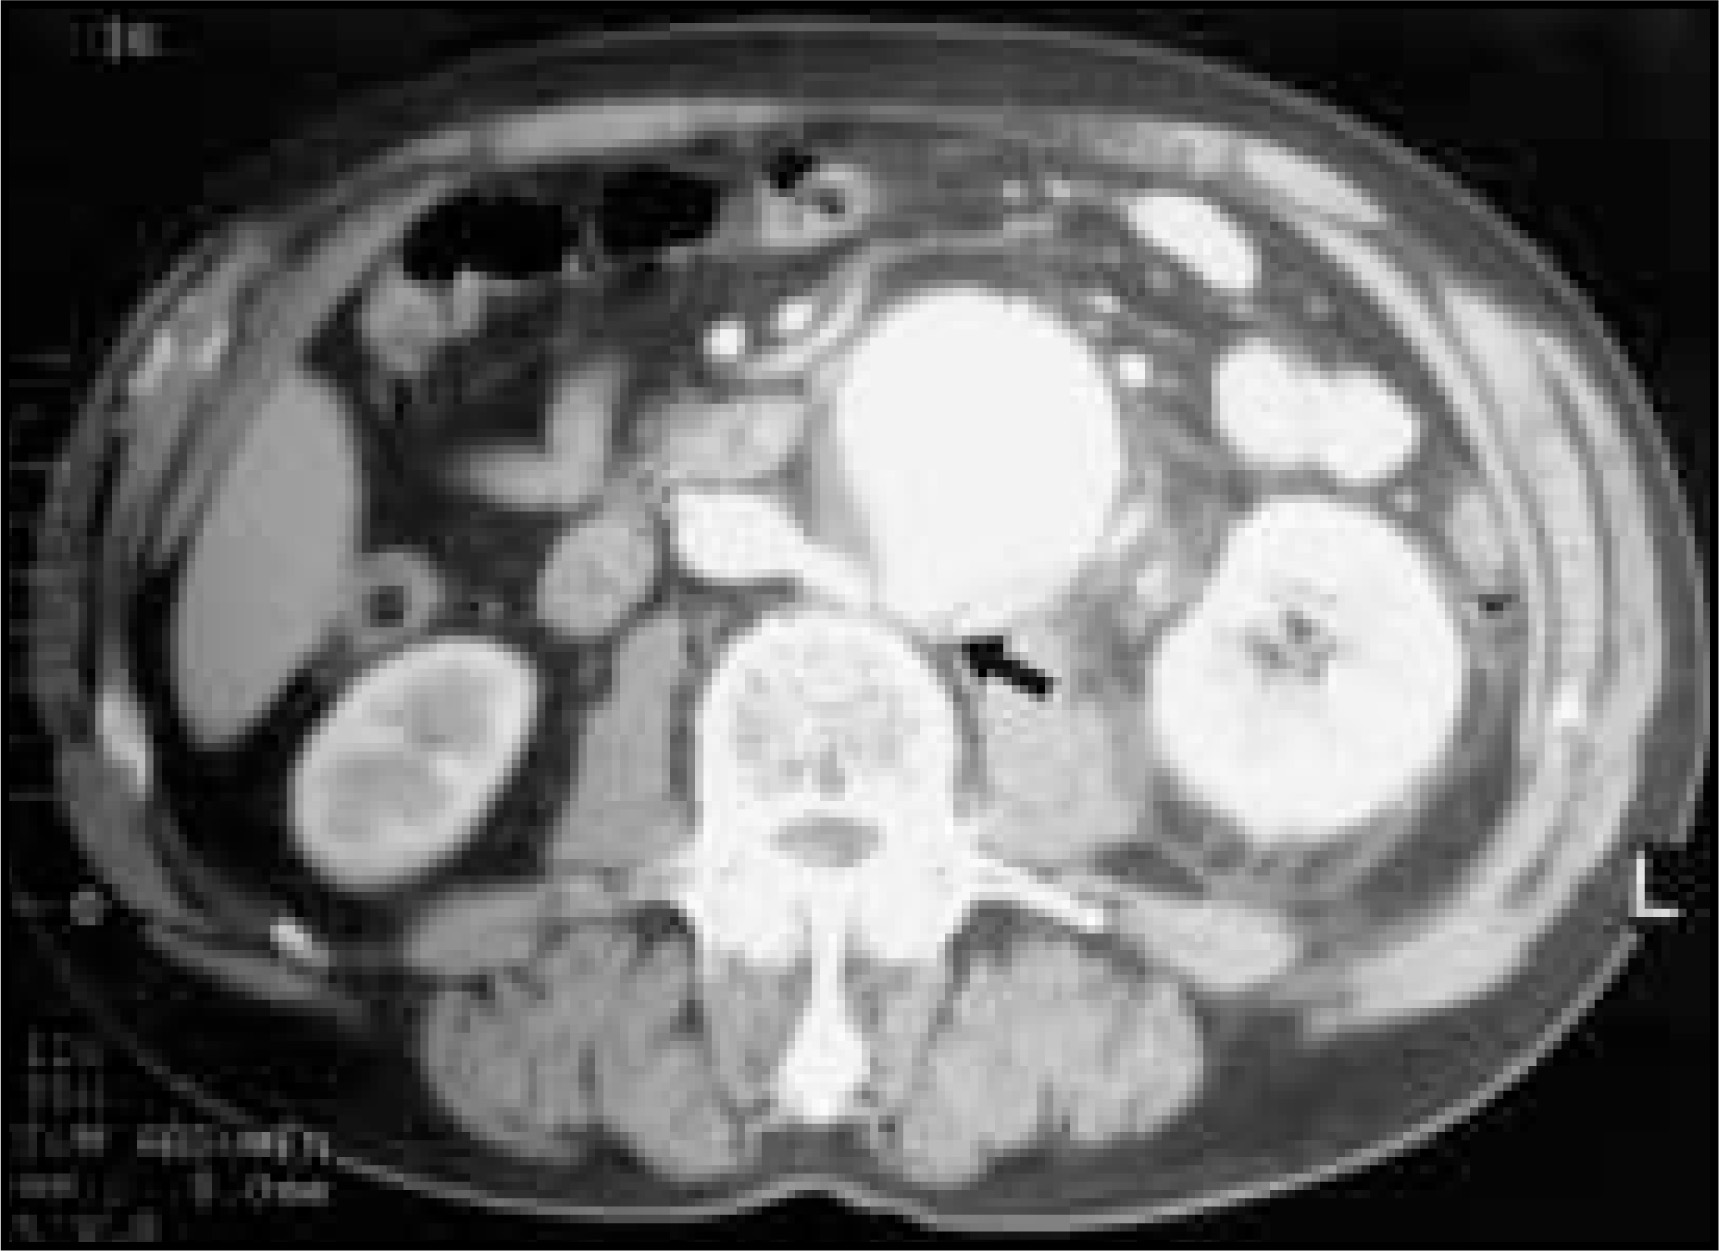
Five days later, the patient developed an elevated serum creatinine level as well as high-output congestive failure. Another CT of the abdomen was performed (Figure 2) that demonstrated opacification of the aorta, inferior vena cava (IVC), and left renal vein to the same degree with intravenous contrast with near absent perfusion of the left kidney.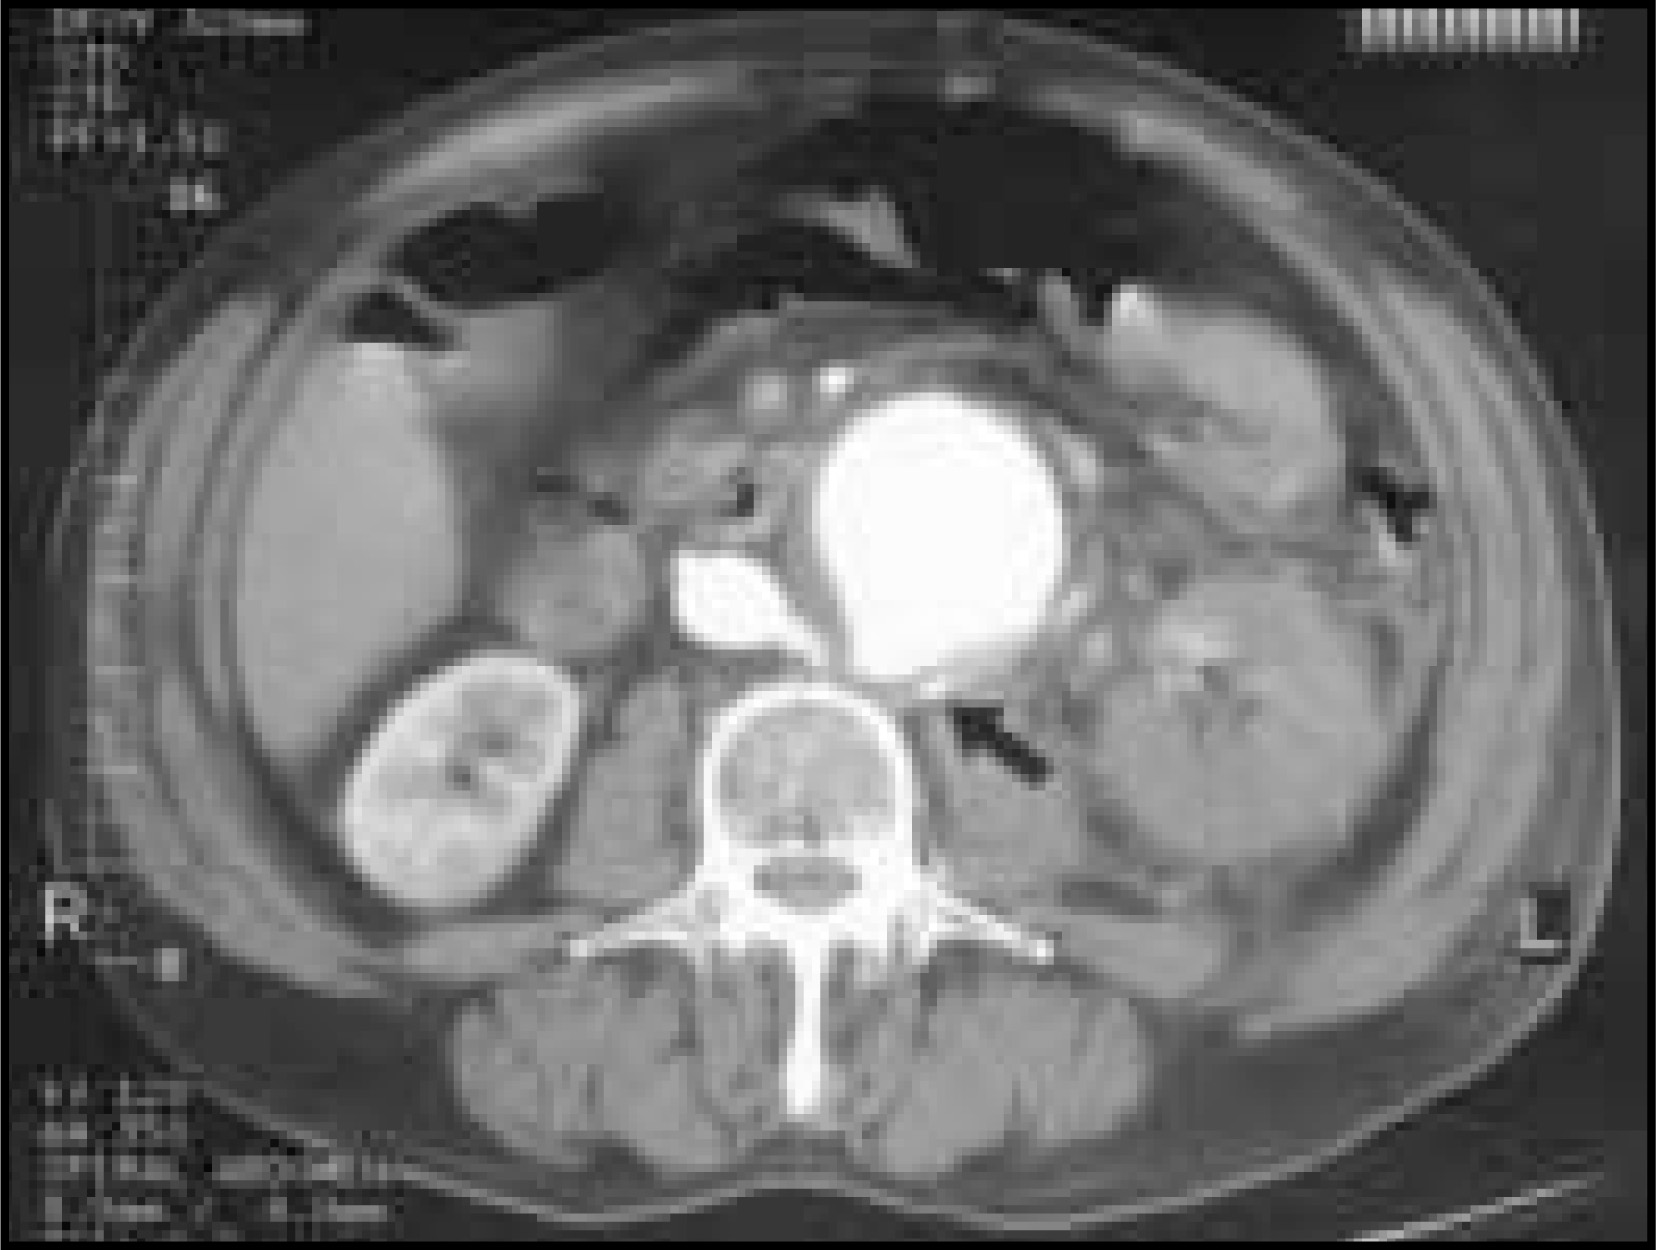
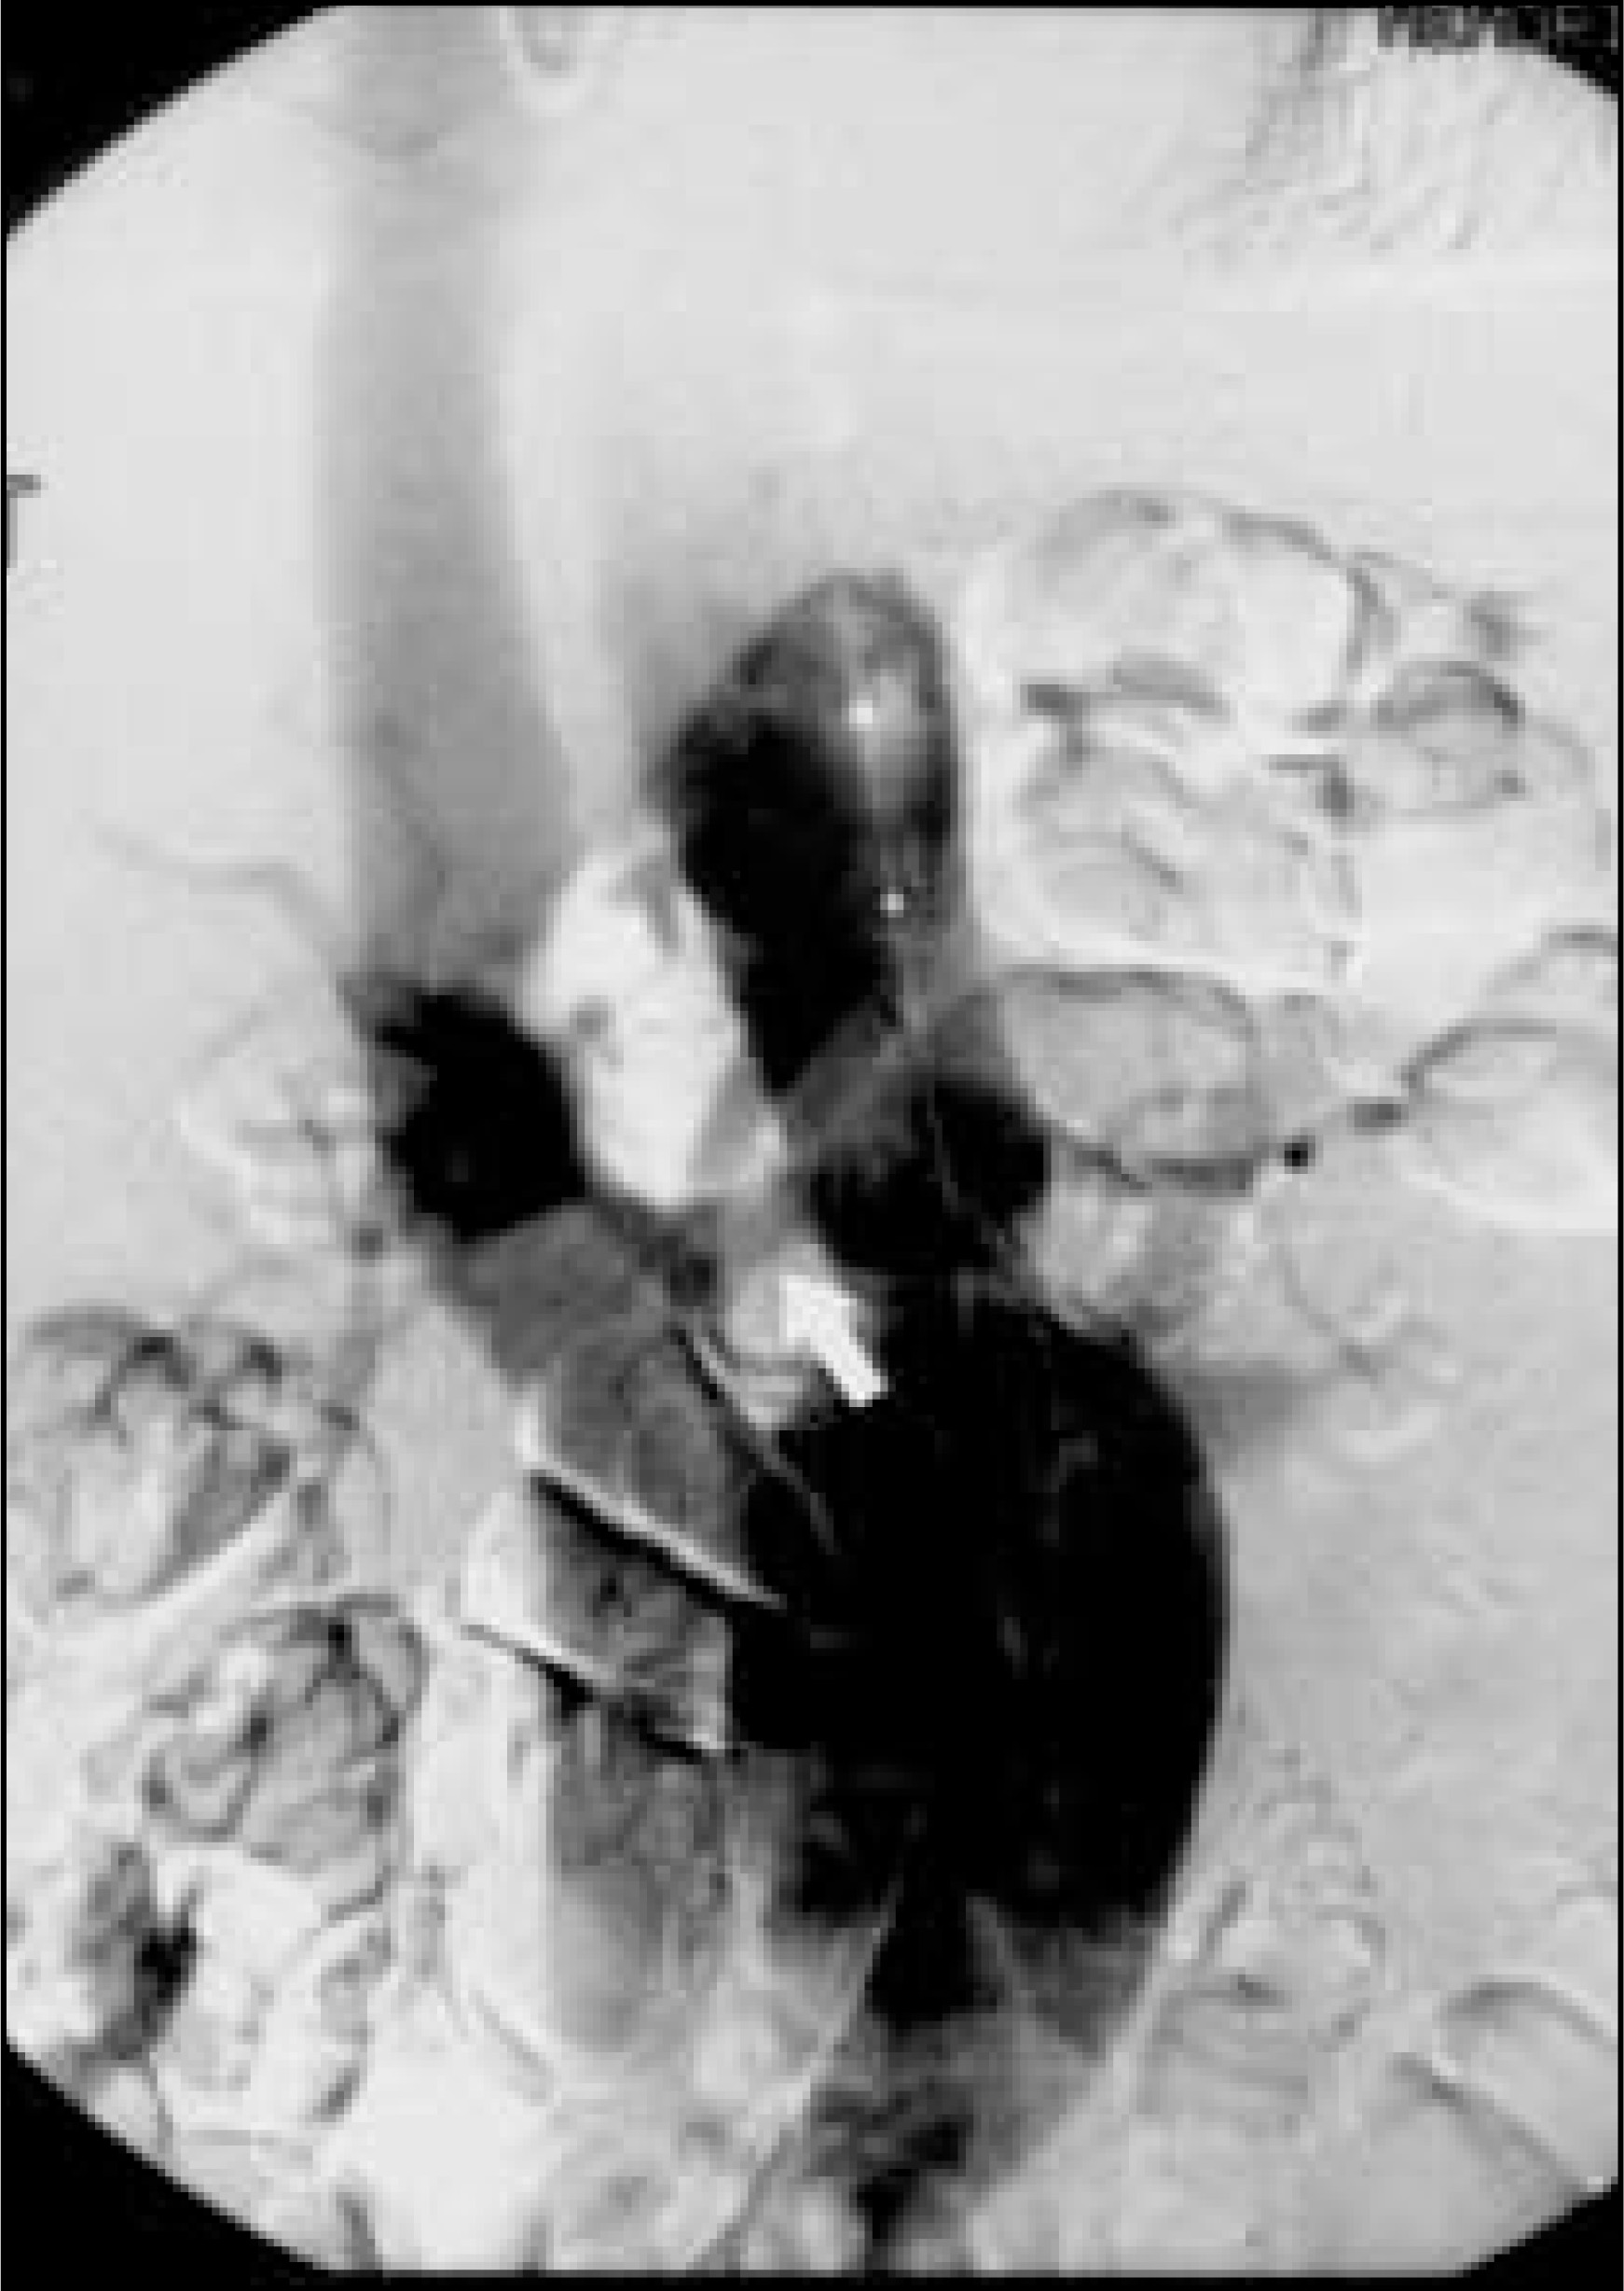
The patient underwent aortography. A floppy J-wire was inserted through the aortic aneurysm into the left renal vein and subsequently into the IVC (Figure 3). Following contrast administration, there was rapid visualization of the left renal vein as well as the IVC (Figure 4).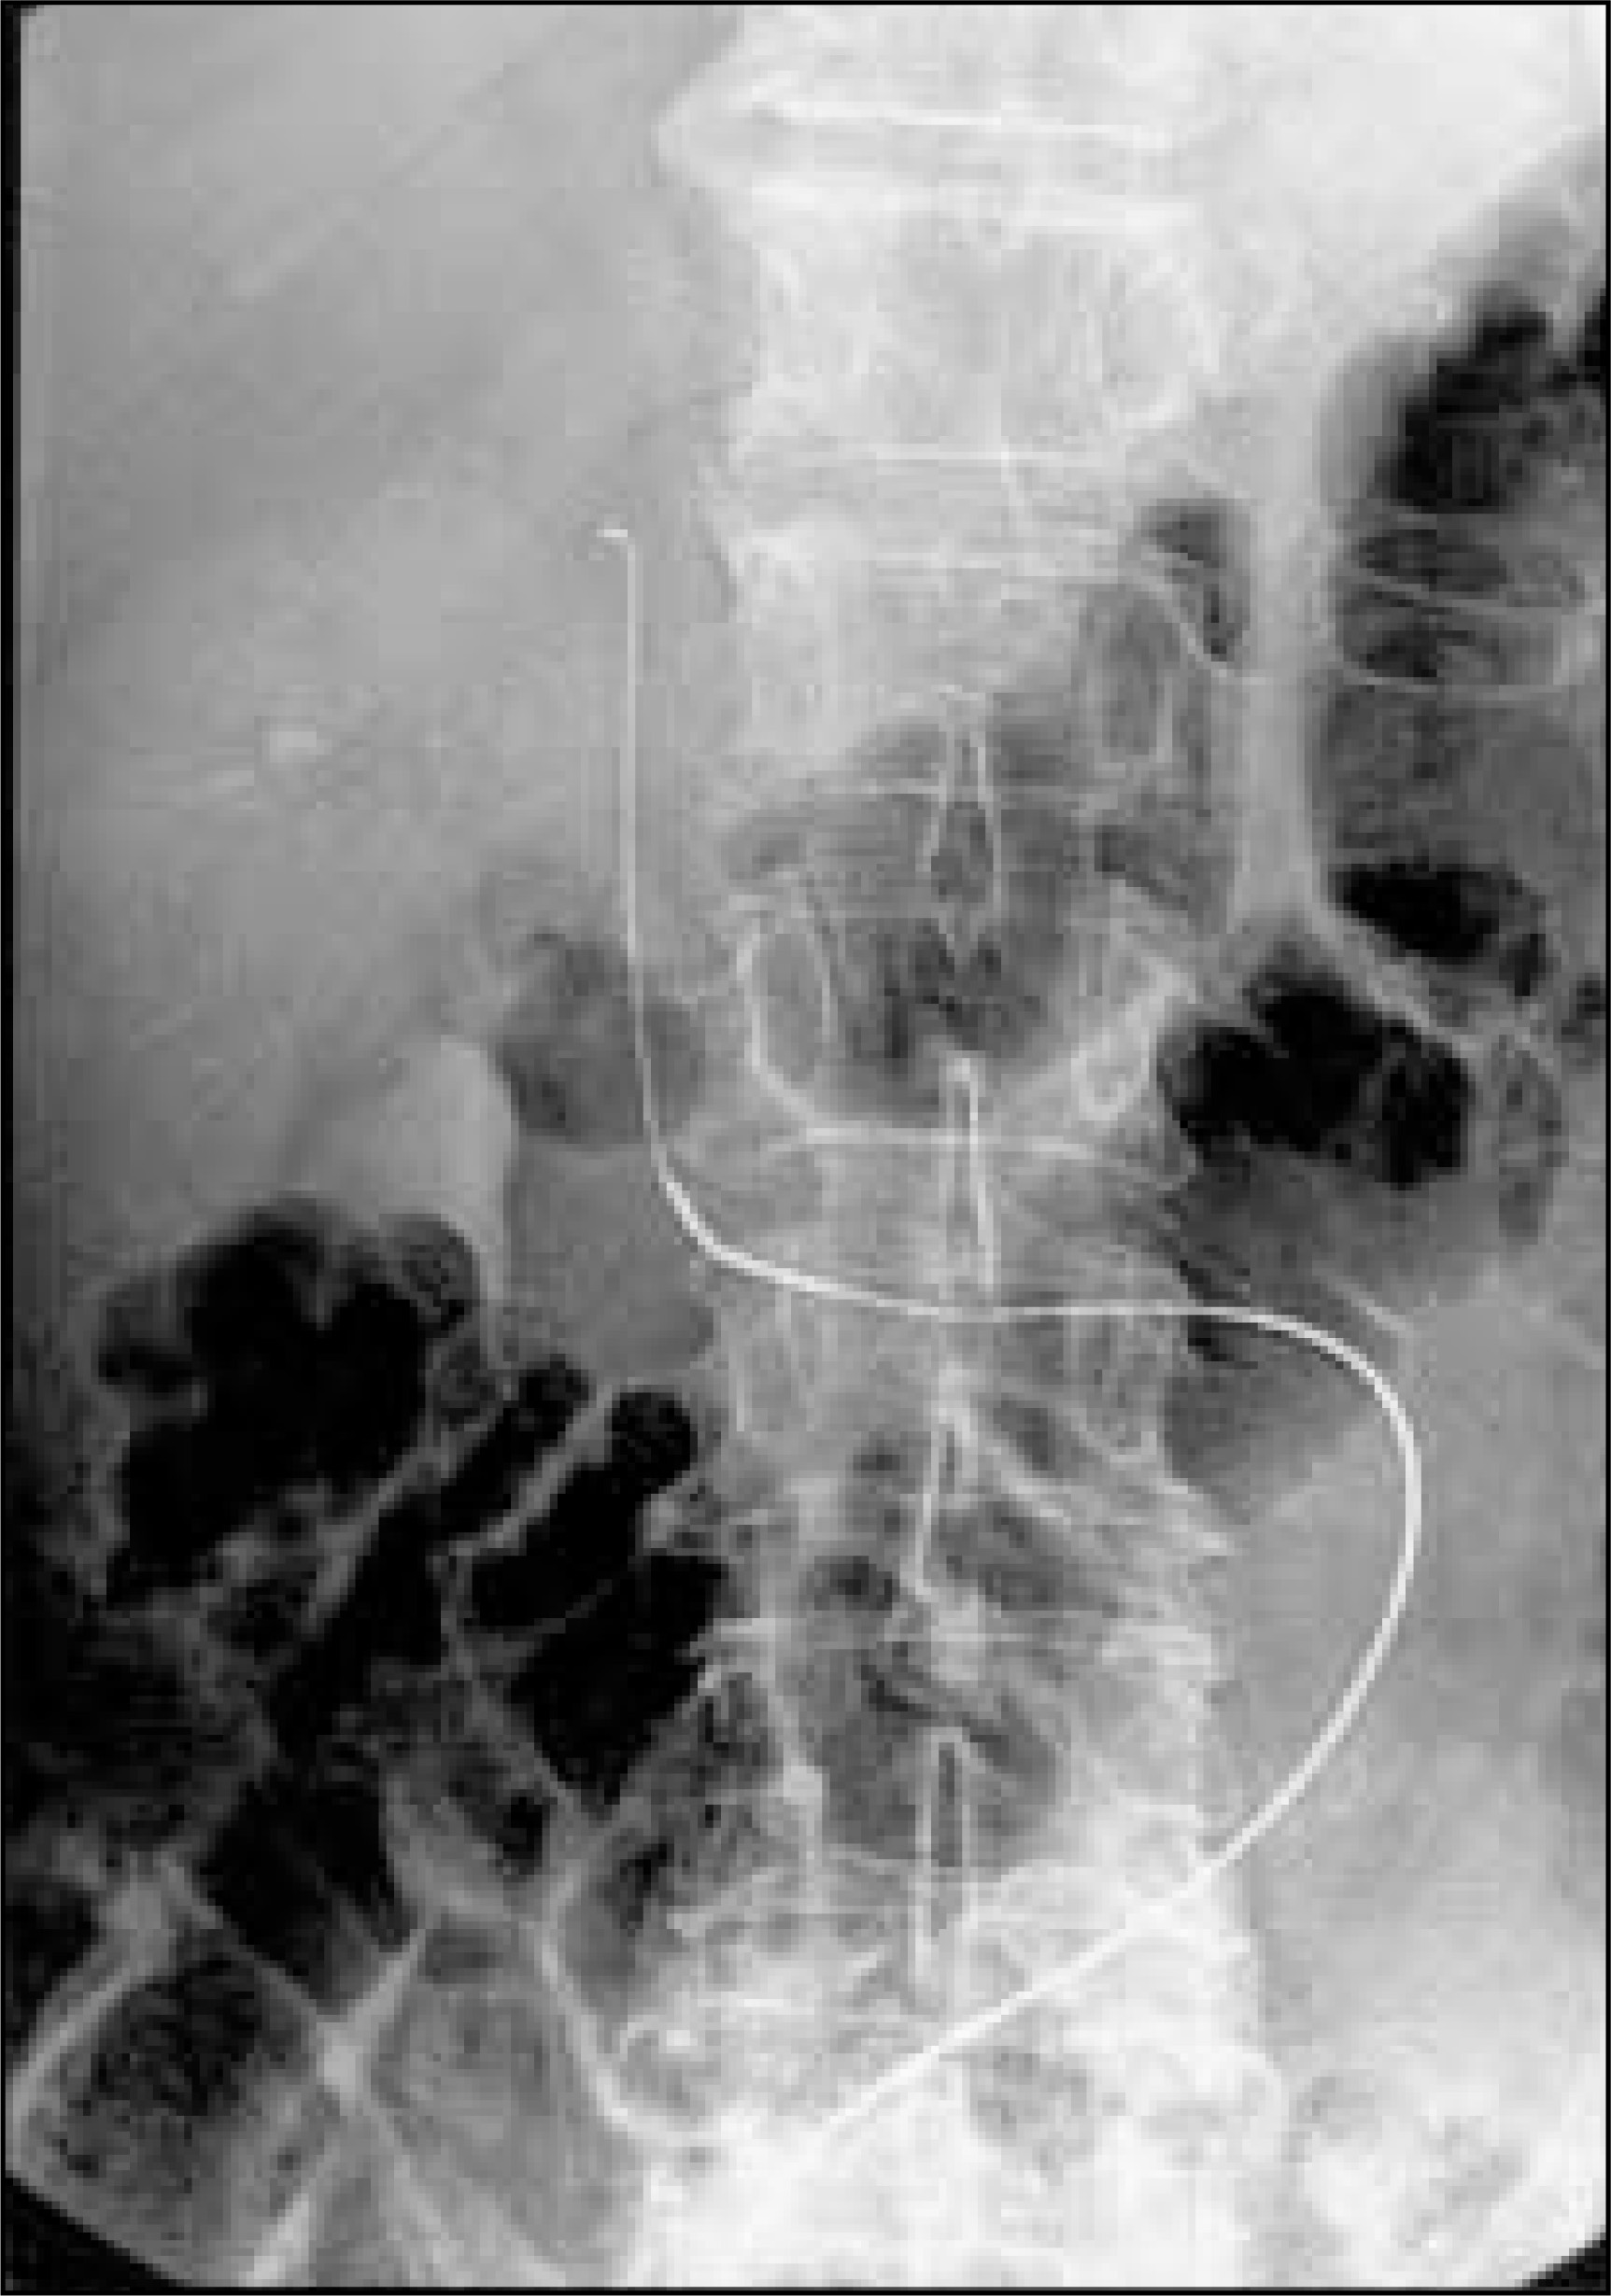
DIAGNOSIS
Spontaneous aorta-left renal vein fistula
IMAGING FINDINGS
An abdominal CT obtained upon the patient’s initial presentation to an outside facility shows a fusiform abdominal aortic aneurysm with focal contour deformity posteriorly, anterior to a retroaortic left renal vein (Figure 1). There is contrast opacification of the aorta, left renal vein, and IVC to the same degree; both kidneys are perfused. A second abdominal CT obtained 5 days following the initial presentation again reveals focal contour abnormality of the posterior abdominal aortic aneurysm directly anterior to the left renal vein with enhancement of the aorta, IVC, and left renal vein to the same degree; however, the left kidney is now minimally perfused (Figure 2). An abdominal aortogram obtained upon presentation to our facility demonstrates passage of a wire into the right femoral artery, through the fistula, into the left renal vein and, finally, into the IVC (Figure 3). Contrast injected into the upper abdominal aorta is immediately seen within the aorta, left renal vein, and IVC simultaneously, showing the fistula between the aorta and left renal vein (Figure 4).
DISCUSSION
Many complications of abdominal aortic aneurysm have been described, the most common being rupture. A less commonly described complication is the development of a fistula from the enlarged aorta to other nearby structures. A number of cases of aorta-caval fistulas have been described in medical literature. Iliac vein and enteric fistulas have also been described. Other vascular communications are far less common. This case demonstrates the spontaneous development of a fistula between an abdominal aortic aneurysm and a retroaortic left renal vein. An English literature search revealed only 20 reported cases1-19 of spontaneous aorta-left renal vein fistula; however, none of these reports indicated the evolution of such a fistula with radiographic imaging. Almost all of these patients had a retroaortic left renal vein.1
Prior reports have described a clinical syndrome of abdominal pain, pulsatile abdominal mass, elevated serum creatinine, hematuria, and nonperfusion of the left kidney on imaging studies.2 Often, as serum creatinine rises due to nonperfusion of the left kidney, treatment is delayed as a primary renal problem is suspected.3 Also, physicians are reluctant to perform a CT of the abdomen with contrast due to poor renal function, again delaying the diagnosis.
Sultan et al20 describe an attempt at endovascular repair with a stent graft that, although it was unsuccessful in that particular case, suggests a minimally invasive approach might be used in the future.
CONCLUSION
Although an aorta-left renal vein fistula is a rare entity, this diagnosis must be suspected in a patient with abdominal aortic aneurysm, hematuria, and worsening renal function. Also, endovascular repair should be considered, especially in patients with a high surgical risk.
References
- Meyerson S, Haider S, Gupta N. Abdominal aortic aneurysm with aorta-left renal vein fistula with left varicocele. J Vasc Surg. 2000;31:307-313.
- Thompson R, Yee L, Natuzzi E, Stoney R. Aorta-left renal vein fistula syndrome caused by rupture of a juxtarenal abdominal aortic aneurysm: Novel pathologic mechanism for a unique clinical entity. J Vasc Surg. 1993;18:310-315.
- Katz S, Kohl R. Spontaneous rupture of an aortic aneurysm into the left renal vein. A diagnostic challenge. J Cardiovasc Surg. 1990;31:479-481.
- Madhavan P, Sproule J, Blake M. Aorta-left renal vein fistula: An unusual complication of an abdominal aortic aneurysm. Eur J Vasc Endovasc Surg. 1999;17:87-88.
- Jabbour N, Radulescu O, Flogiates T, Stahl W. Hemodynamics of an aorta-left renal vein fistula: A case report and a review of the literature. Crit Care Med. 1993;21:1092-1095.
- Hoballah J, Chalmers R, Sharp W. Aortic aneurysm rupture into a retroaortic left renal vein. Ann Vasc Surg. 1993;7:363-367.
- Mansour M, Rutherford R, Metcalf R, Pearce W. Spontaneous aorta-left renal vein fistula: The “abdominal pain, hematuria, silent left kidney” syndrome. Surgery. 1999;109:101-106.
- Calligaro K, Savarese R, DeLauretis D. Unusual aspects of aortovenous fistulas associated with ruptured abdominal aortic aneurysms. J Vasc Surg. 1990;12:586-590.
- Mansour M, Russ P, Subber S, Pearce W. Aorto-left renal vein fistula: Diagnosis by duplex sonography. AJR Am J Roentgenol. 1989;152:1107-1108.
- Celoria G, Friedman P, Rhee S, Berman J. Fistulas between the aorta and left renal vein. J Vasc Surg. 1987;6:191-193.
- Linsell J, Rowe P, Owen W. Rupture of an aortic aneurysm into the renal vein presenting as a left-sided varicocele. Case report. Acta Chir Scand. 1987;153:477-478.
- Mercurias-Taylor L, Kurer M. Haematuria and abdominal aortic aneurysm. J Cardiovasc Surg. 1986;27:565-567.
- Heier L, Saibil E, Blair G, Maggisano R. Angiographic demonstration of an aorta-left renal vein fistula. J Can Assoc Radiol. 1984;35:322-323.
- Harjula A, Luosto R, Konttinen M. Fistula between abdominal aortic aneurysm and left renal vein. Acta Chir Scand. 1983;149:541-544.
- Gourdin F, Salam A, Smith R, Perdue G. Aortovenous fistulas due to ruptured infrarenal aortic aneurysms: Experience with six cases. South Med J. 1982;75:913-916.
- Suzuki M, Collins G, Bassinger G, Dilley R. Aorto-left renal vein fistula: An unusual complication of abdominal aortic aneurysm. Ann Surg. 1976;184:31-34.
- Yashar J, Hallman G, Cooley D. Fistula between aneurysm of aorta and left renal vein. Report of a case. Arch Surg. 1969;99:546-548.
- Horan D, Sharp J. Spontaneous fistula between the aorta and left renal vein. Am J Surg. 1967;113:802-806.
- Lord J, Vigorita J, Flioro J. Fistula between abdominal aortic aneurysm and anomalous renal vein. JAMA. 1964;187:535-536.
- Sultan S, Madhavan P, Colgan M. Aorto-left renal vein fistula: Is there a place for endovascular management?. J Endovasc Surg. 1999;6:375-377.
Citation
. RCOM RADIOLOGICAL CASE OF THE MONTH. Applied Radiology. 2004;33(2):37-39. doi:10.37549/AR1222.