RCOM RADIOLOGICAL CASE OF THE MONTH
Applied Radiology — Vol. 33 , Issue 9 , pp. 46 -49
DOI: 10.37549/AR1279
Published: September 1, 2004
1 Albany Medical College, Albany, NY
Categories
CASE SUMMARY
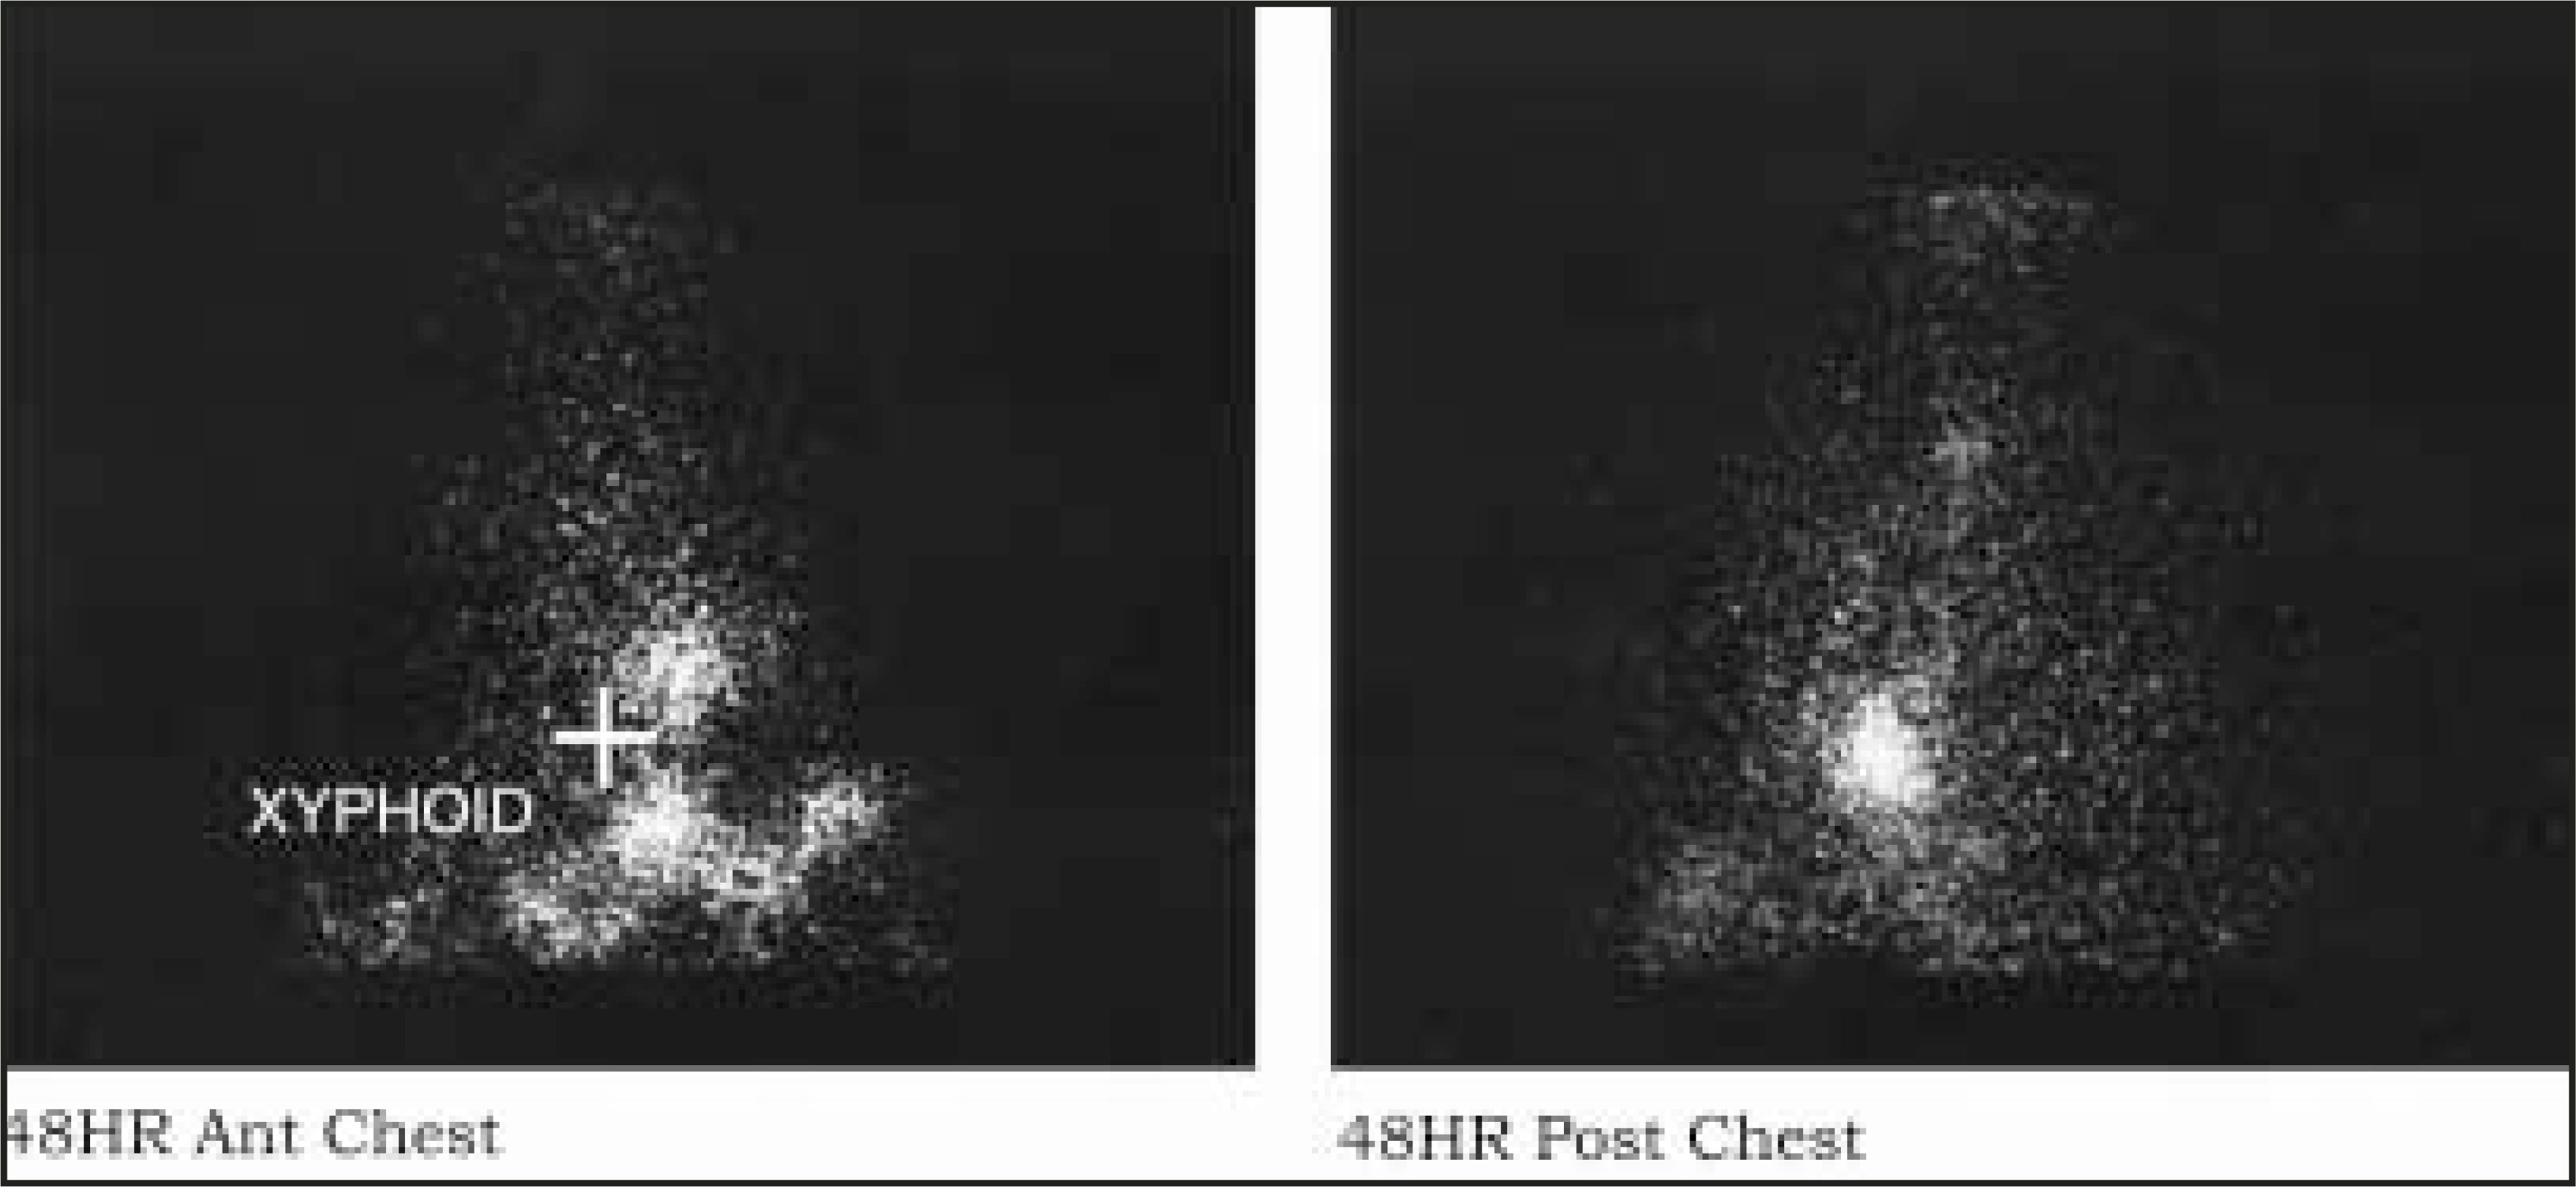
A 76-year-old man presented to the nuclear medicine department for a follow-up whole-body iodine-131 (I-131) scan in February 2002 (Figures 1 and 2). This was prompted by a rising serum thyroglobulin measured at 6.6 ng/mL under suppression and 17.2 ng/mL after thyroid withdrawal. He had initially undergone near total thyroidectomy for papillary thyroid carcinoma (2-cm mass) in October 1993, followed by ablation with 150 mCi of I-131 in December 1993. Preablation and 1-week-postablation scans showed 2 foci of uptake in the neck, suggestive of remnant thyroid tissue. A follow-up scan obtained in 1994 showed no abnormal foci of uptake of I-131, suggesting complete ablation of the thyroid remnant.The patient was followed with serial thyroglobulins only, between 1994 and 2002.

DIAGNOSIS
Metastatic thyroid cancer
IMAGING FINDINGS
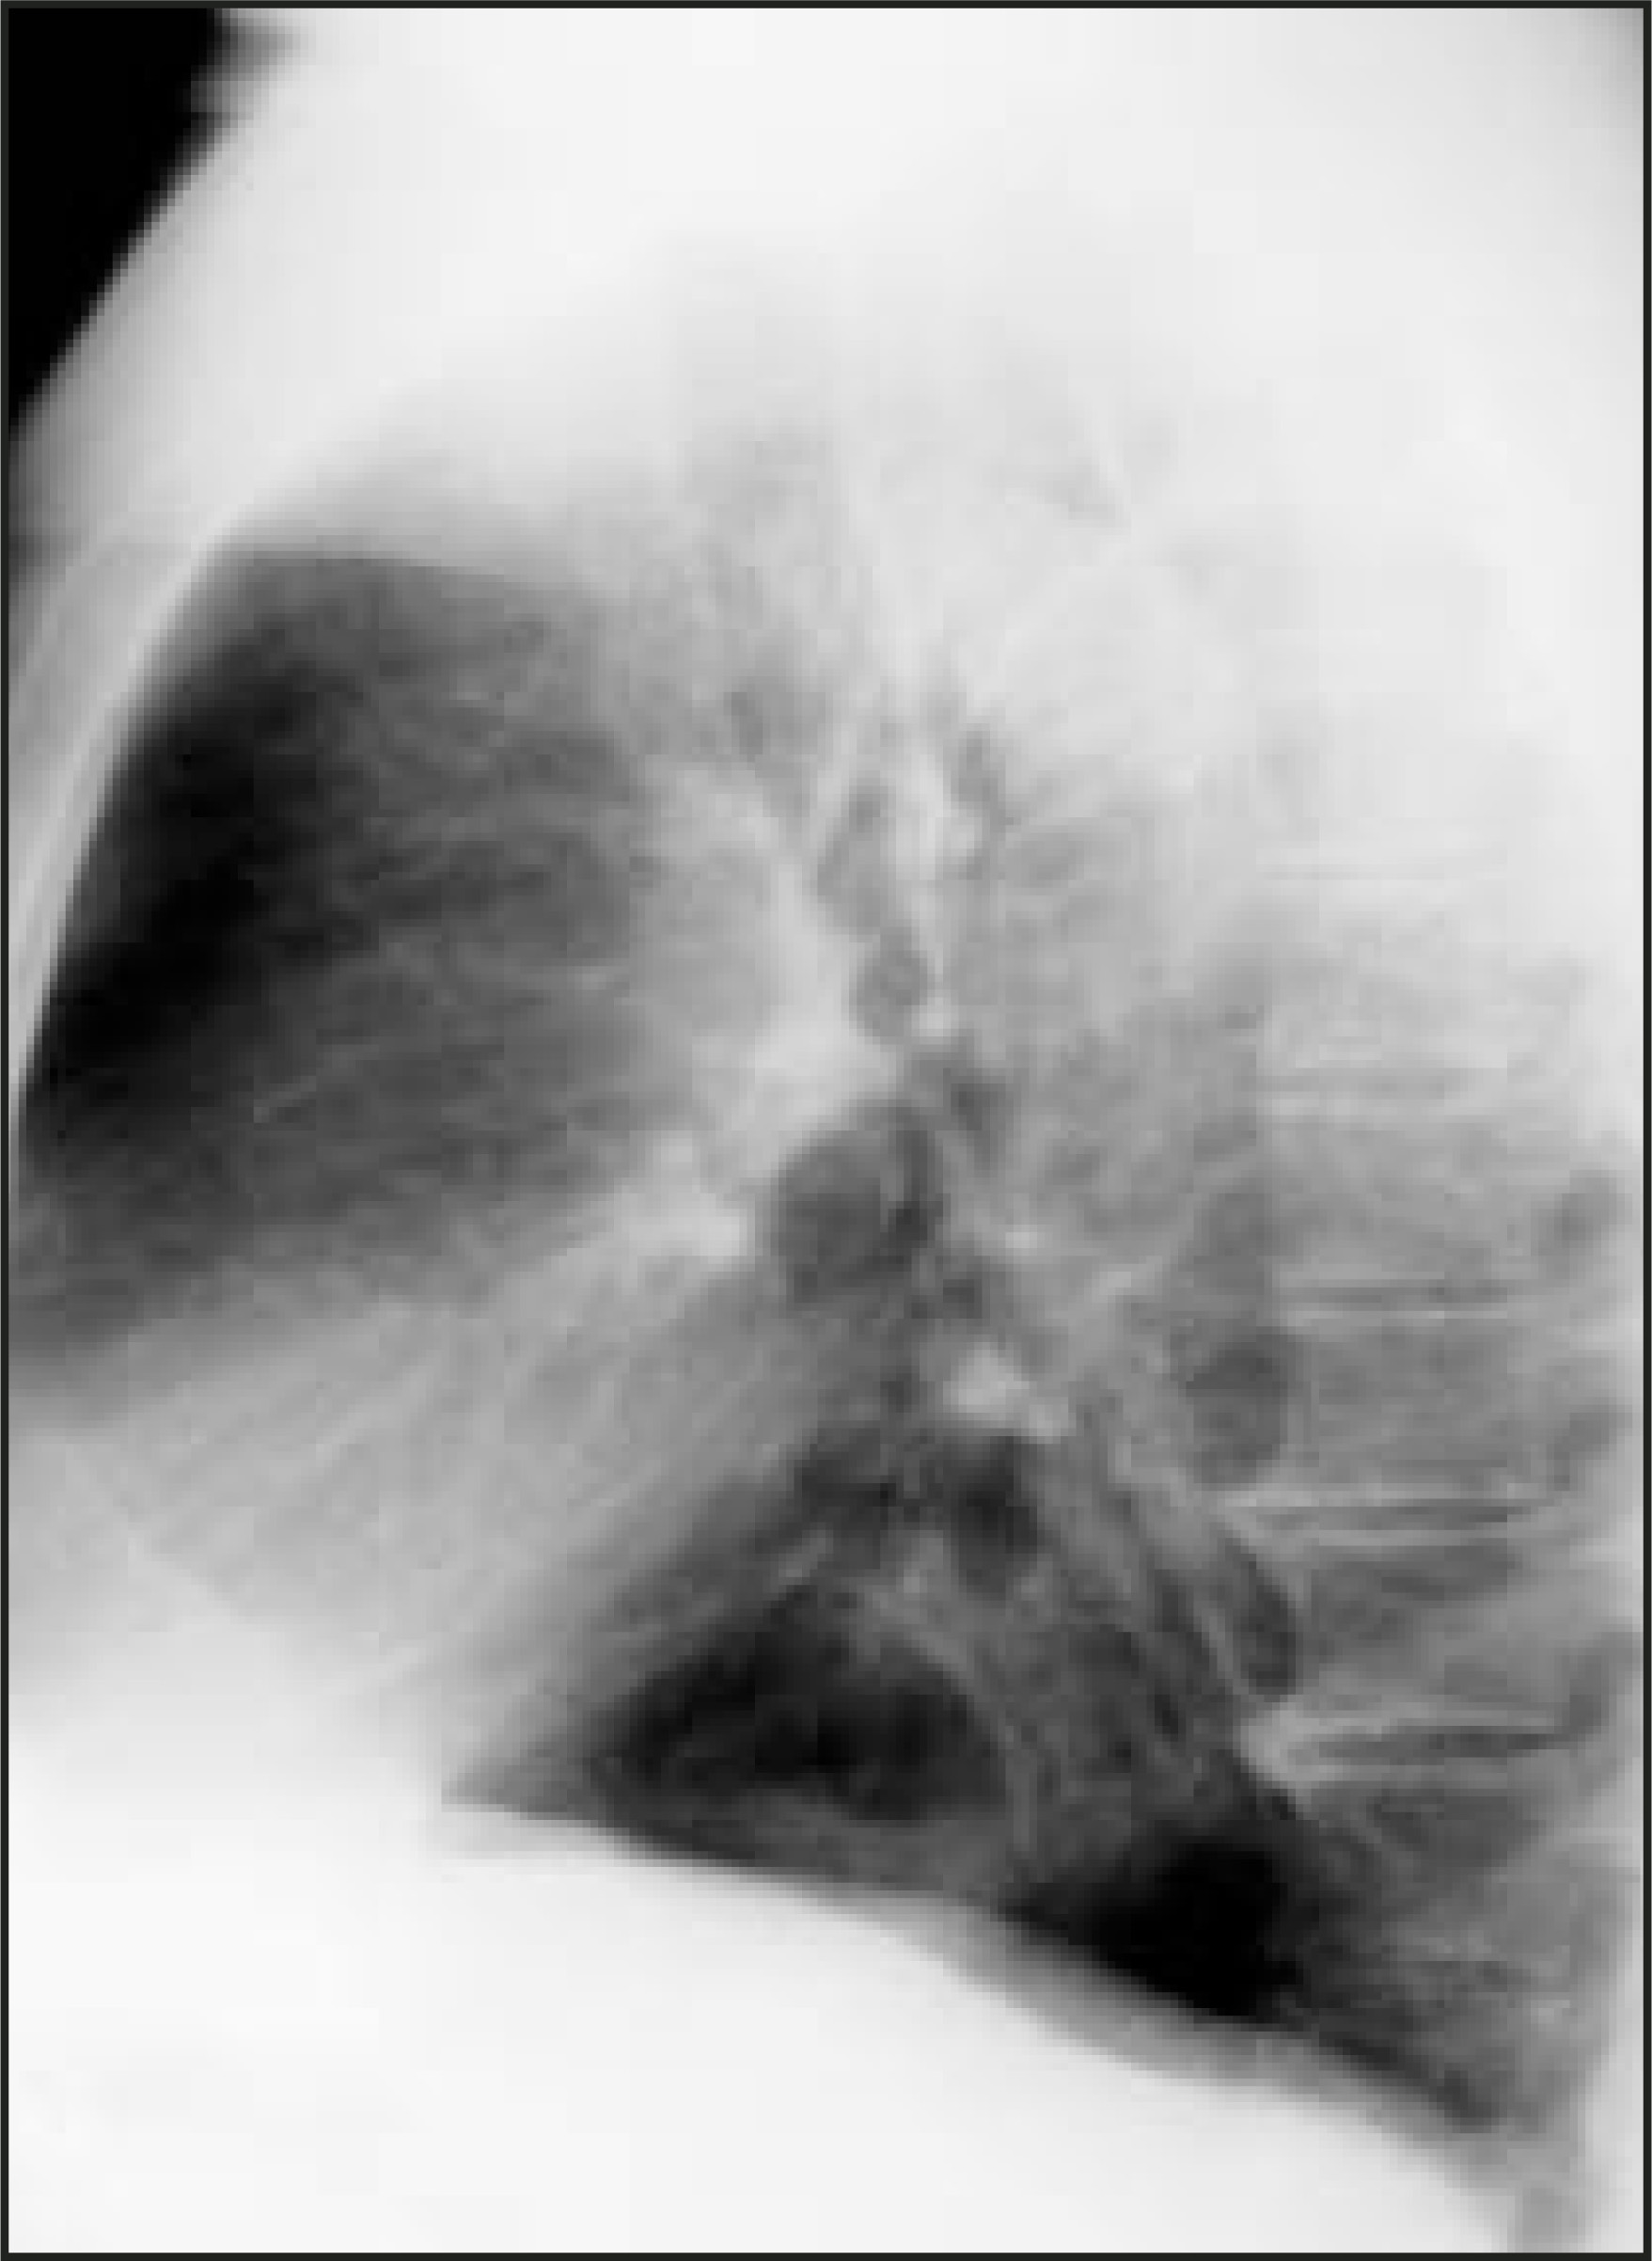
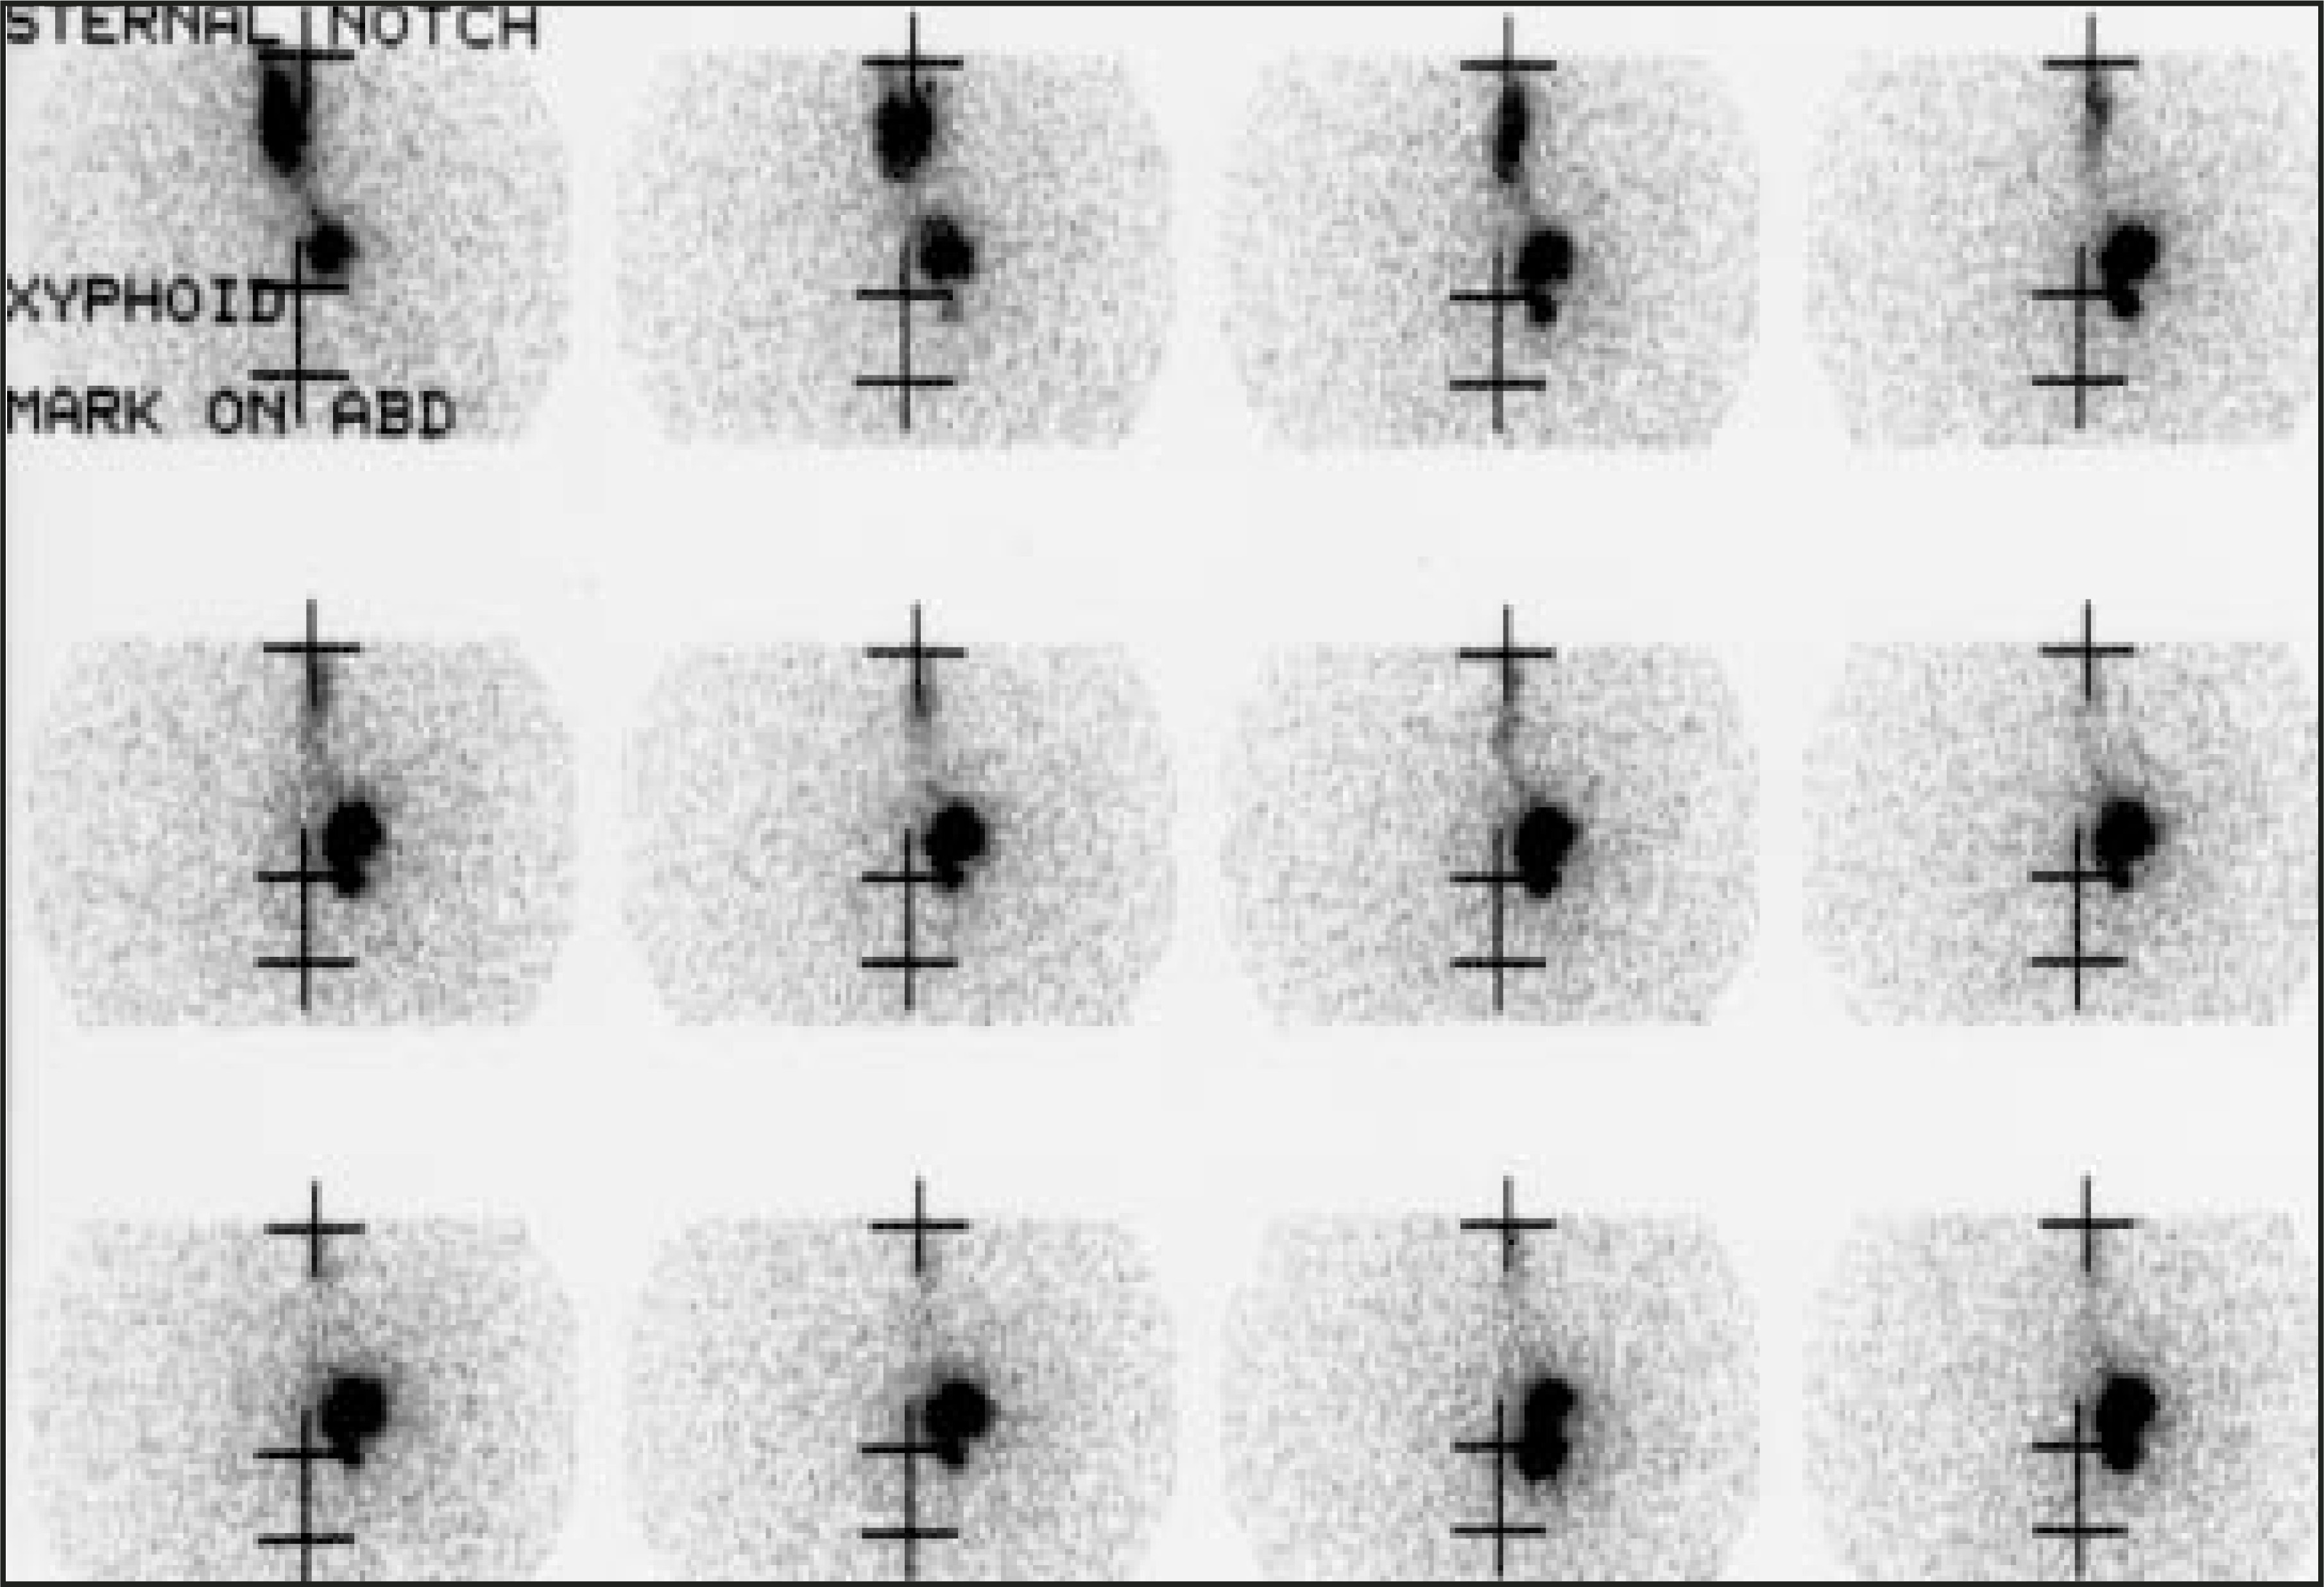
The 2002 I-131 whole-body scan showed a midline focus of uptake in the chest, which was suspected to be mediastinal metastases (Figures 1 and 2). The patient had a known hiatal hernia that had been detected on a chest radiograph (Figure 3), and physiological uptake by a displaced gastric mucosa was suspected. Technetium (Tc)-99m pertechnetate, administered orally, showed an ectopic gastric focus of uptake, identical in location to that seen on the radioiodine scan (Figure 4), and confirmed the suspicion. The patient was re-treated with 150 mCi of I-131 because of the elevated thyroglobulin. The 1-week-postablation scan (Figure 5) showed a new focus of uptake in the left supraclavicular area, highly suggestive of metastatic disease. A computed tomography (CT) of the neck (not shown) was negative for enlarged lymph nodes or a soft-tis-sue mass. A repeat thyroglobulin level under suppression (TSH = 0.07) was obtained 6 months later, which was 6.1 ng/mL, suggesting failure of the blind I-131 therapy.

DISCUSSION
This case illustrates a false-positive finding on a radioiodine whole-body scan and invites caution in interpretation of this study. Excellent reviews describing in detail all possible causes of false-positive findings have been published elsewhere,1,2 and are beyond the scope of this case report. Overall, the whole-body scan has a very high specificity that is reported to be in the range of 98% to 100%.1 In the chest, false-positive uptake may be due to external contamination,3 retention of secretions in the esophagus or trachea,4 or pathologic activity unrelated to thyroid carcinoma, such as lung or pericardial disease.5,6 More relevant to this case, occasional cases have been reported of uptake in ectopic or displaced gastric mucosa, such as hiatal hernia,7 postgastric pull-up,8 or Barrett’s esophagus.9 Although hiatal hernia is a relatively common condition, it is surprising that it has rarely been reported as a cause of a false-positive whole-body scan. When the scan shows uptake in the chest, a chest radiograph may be useful. In addition, dynamic imaging using oral Tc-99m pertechnetate or Tc-99m sulfur colloid will readily illustrate the descent of the bolus from the esophagus to the stomach and may identify ectopic gastric mucosa as the etiology for the chest uptake.
The occurrence of a negative diagnostic scan in the presence of an elevated thyroglobulin is more frequent than a false-positive study and poses a management problem to the practicing nuclear medicine physician. The incidence of false-negative studies has been reported to be between 5% and 25%.10-12 The variability in results may be due to patient population or to the assay used to measure thyroglobulin. The most recent publications indicate that the incidence is closer to 25%.13 It is also likely that, as the assay becomes more and more sensitive and as the cutoff value for detectable thyroglobulin decreases, the incidence of false-negative scans will increase.
One management approach to this subset of patients with false-negative scans would be to treat them anyway with high ablative doses of I131. This approach is commonly adopted today and offers two advantages. The first is that scanning after therapy will demonstrate foci of tracer uptake that have not been visualized on a corresponding low-dose pretherapy scan in 10% to 30% of cases.14 However, the incremental diagnostic value of posttreatment scans has not been studied rigorously. The second is that a therapeutic response has been observed in such cases, as documented by a declining thyroglobulin level. However, the response has neither been universal nor complete.15 The case reported here is an illustrative example of poor response to I-131, since the suppressed thyroglobulin level decreased from 6.6 ng/mL before therapy to 6.1 ng/mL after therapy.
One alternative approach would be to withhold treatment with I-131 and examine the patient with another imaging modality to search for the site of recurrence. The advantage of this approach would be that identification of focal and accessible disease would lead to surgical excision. Such therapy is radical and more likely to succeed than is radioiodine in this setting, since a negative diagnostic scan indicates that malignant thyroid cells are not iodine-avid and, therefore, not very sensitive to ablation. In order for this strategy to succeed, the new imaging modality should have a high sensitivity for detecting recurrence.
Fluorodeoxyglucose positron emission tomographic (FDG-PET) imaging appears to fulfill these requirements. In a study by Helal and associates,16 FDG-PET imaging was compared prospectively with other conventional imaging procedures (chest radiography, ultrasonography, magnetic resonance imaging, CT, and bone scintigraphy) in 37 patients with well-differentiated thyroid carcinoma. All patients had an elevated thyroglobulin and a negative postablation scan. Only 10 of 37 patients had a positive study using a conventional procedure. In this group, FDG-PET imaging confirmed 17 of 18 previously known tumor sites and detected 11 additional sites. In the remaining 27 with negative conventional studies, FDGPET imaging was positive in 19. Overall, the FDG data led to a change in the management of 29 of 37 patients. Specifically, surgical resection was performed in 23 patients, 14 of whom achieved disease-free status. Similar results have been reported by other investigators.17-19 For instance, Frilling et al18 found that the sensitivity of the method in the subset of patients with negative whole-body scan and elevated thyroglobulin was 94.6%. Fein et al19 found an inverse relationship between I-131 and FDG uptake that would make PET imaging ideally suited to this population. In addition, it may provide prognostic information, since patients with FDG-avid lesions appear to follow a more aggressive course.20
CONCLUSION
A thorough knowledge of potential causes of false-positive findings is important for the accurate interpretation of radioiodine whole-body scans, as illustrated by this case. The occurrence of false-negative scans is more frequent and more difficult to address. Blind administration of high doses of I-131 may not produce the best results. The recent availability and approval of FDG-PET imaging may provide the opportunity for an alternative diagnostic and management approach. Prospective comparative studies of the two approaches and their long-term outcomes are needed.
References
- McDougall R. Whole-body scintigraphy with radioiodine-131: A comprehensive list of false-positives with some examples. Clin Nucl Med. 1995;20:869-875.
- Shapiro B, Rufini V, Jarwan A. Artifacts, anatomical and physiological variants, and unrelated diseases that might cause false-positive whole-body 131-I scans in patients with thyroid cancer. Semin Nucl Med. 2000;30:115-132.
- Bakheet S, Powe J, Hammami M. Radioiodine uptake in the chest. J Nucl Med. 1997;38:984-986.
- Schuster D, Alazraki N. Esophageal scarring causing false-positive uptake on I-131 whole-body imaging. Clin Nucl Med. 1998;23:334.
- Haubold-Reuter B, Landolt U, Schulthess G. Bronchogenic carcinoma mimicking metastatic thyroid carcinoma. J Nucl Med. 1993;34:809-811.
- Geatti O, Shapiro B, Orsolon P. An unusual false-positive scan in a patient with pericardial effusion. Clin Nucl Med. 1994;19:678-682.
- McNamara M, Tsang H. Hiatal hernia with reflux resulting in false positive iodine-131 scan. Clin Nucl Med. 1998;23:178-179.
- White J, Flickinger F, Morgan M. Iodine-131 accumulation in gastric pull-up simulating pulmonary metastases on total-body scan for thyroid cancer. Clin Nucl Med. 1990;15:809-810.
- Berquist T, Nolan N, Stephens D. Radioisotope scintigraphy in diagnosis of Barrett’s esophagus. AJR Am J Roentgenol. 1971;123:401-411.
- Black E, Sheppard M. Serum thyroglobulin measurements in thyroid cancer: Evaluation of “false” positive results. Clin Endocrinol. 1991;35:519-520.
- Ronga G, Fiorentino A, Fragasso G. Complementary role of whole body scan and serum thyroglobulin determination in the follow-up of differentiated thyroid carcinoma. Ital J Surg Sci. 1986;16:11-15.
- van Sorge-van Boxtel R, Van Eck-Smit B, Goslings B. Comparison of serum thyroglobulin, 131I and 201T1 scintigraphy in the postoperative follow-up of differentiated thyroid cancer. Nucl Med Commun. 1993;14:365-372.
- de Geus-Oei L, Oei H, Hennemann G. Sensitivity of 123I whole-body scan and thyroglobulin in the detection of metastases or recurrent differentiated thyroid cancer. Eur J Nucl Med. 2002;29:768-774.
- Sherman S, Tielens E, Sostre S. Clinical utility of posttreatment radioiodine scans in the management of patients with thyroid carcinoma. J Clin Endocrinol Metab. 1994;78:629-634.
- Pineda J, Lee T, Ain K. Iodine-131 therapy for thyroid cancer patients with elevated thyroglobulin and negative diagnostic scan. J Clin Endocrinol Metab. 1995;80:1488-1492.
- Helal B, Merlet P, Toubert M. Clinical impact of 18F-FDG PET in thyroid carcinoma patients with elevated thyroglobulin levels and negative 131I scanning results after therapy. J Nucl Med. 2001;42:1464-1469.
- Schluter B, Bohuskaviziki K, Beyer W. Impact of FDG PET on patients with differentiated thyroid cancer who present with elevated thyroidglobulin and negative 131I scan. J Nucl Med. 2001;42:71-76.
- Frilling A, Tecklenborg K, Gorges R. Preoperative diagnostic value of [18F] fluorodeoxyglucose positron emission tomography in patients with radiodine-negative recurrent well-dif-ferentiated thyroid carcinoma. Ann Surg. 2001;24:804-811.
- Feine U. Fluor-18-deoxyglucose positron emission tomography differentiated thyroid cancer. Eur J Endocrinol. 1998;138:492-494.
- Wang W, Macapinlac H, Larson S. [18F]-2-fluoro-2-deoxy-D-glucose positron emission tomography localizes residual thyroid cancer in patients with negative diagnostic (131)I whole body scans and elevated serum thyroglobulin levels. J Clin Endocrinol Metab. 1999;84:2291-2302.
Citation
. RCOM RADIOLOGICAL CASE OF THE MONTH. Applied Radiology. 2004;33(9):46-49. doi:10.37549/AR1279.