RCOM RADIOLOGICAL CASE OF THE MONTH
Applied Radiology — Vol. 33 , Issue 11 , pp. 69 -73
DOI: 10.37549/AR1295
Published: November 1, 2004
Categories
CASE SUMMARY
An 86-year-old woman presented with vague abdominal pain and a computed tomographic (CT) study was ordered. Her medical history includes heart failure and hypertension. Her surgical history includes coronary artery bypass graft (CABG) surgery in 1986 and a hysterectomy. An incidental finding was noted on an axial slice from a CT study of the abdomen and pelvis (Figure 1). Further imaging studies were performed, including ultrasound and angiography (Figures 2 through 5).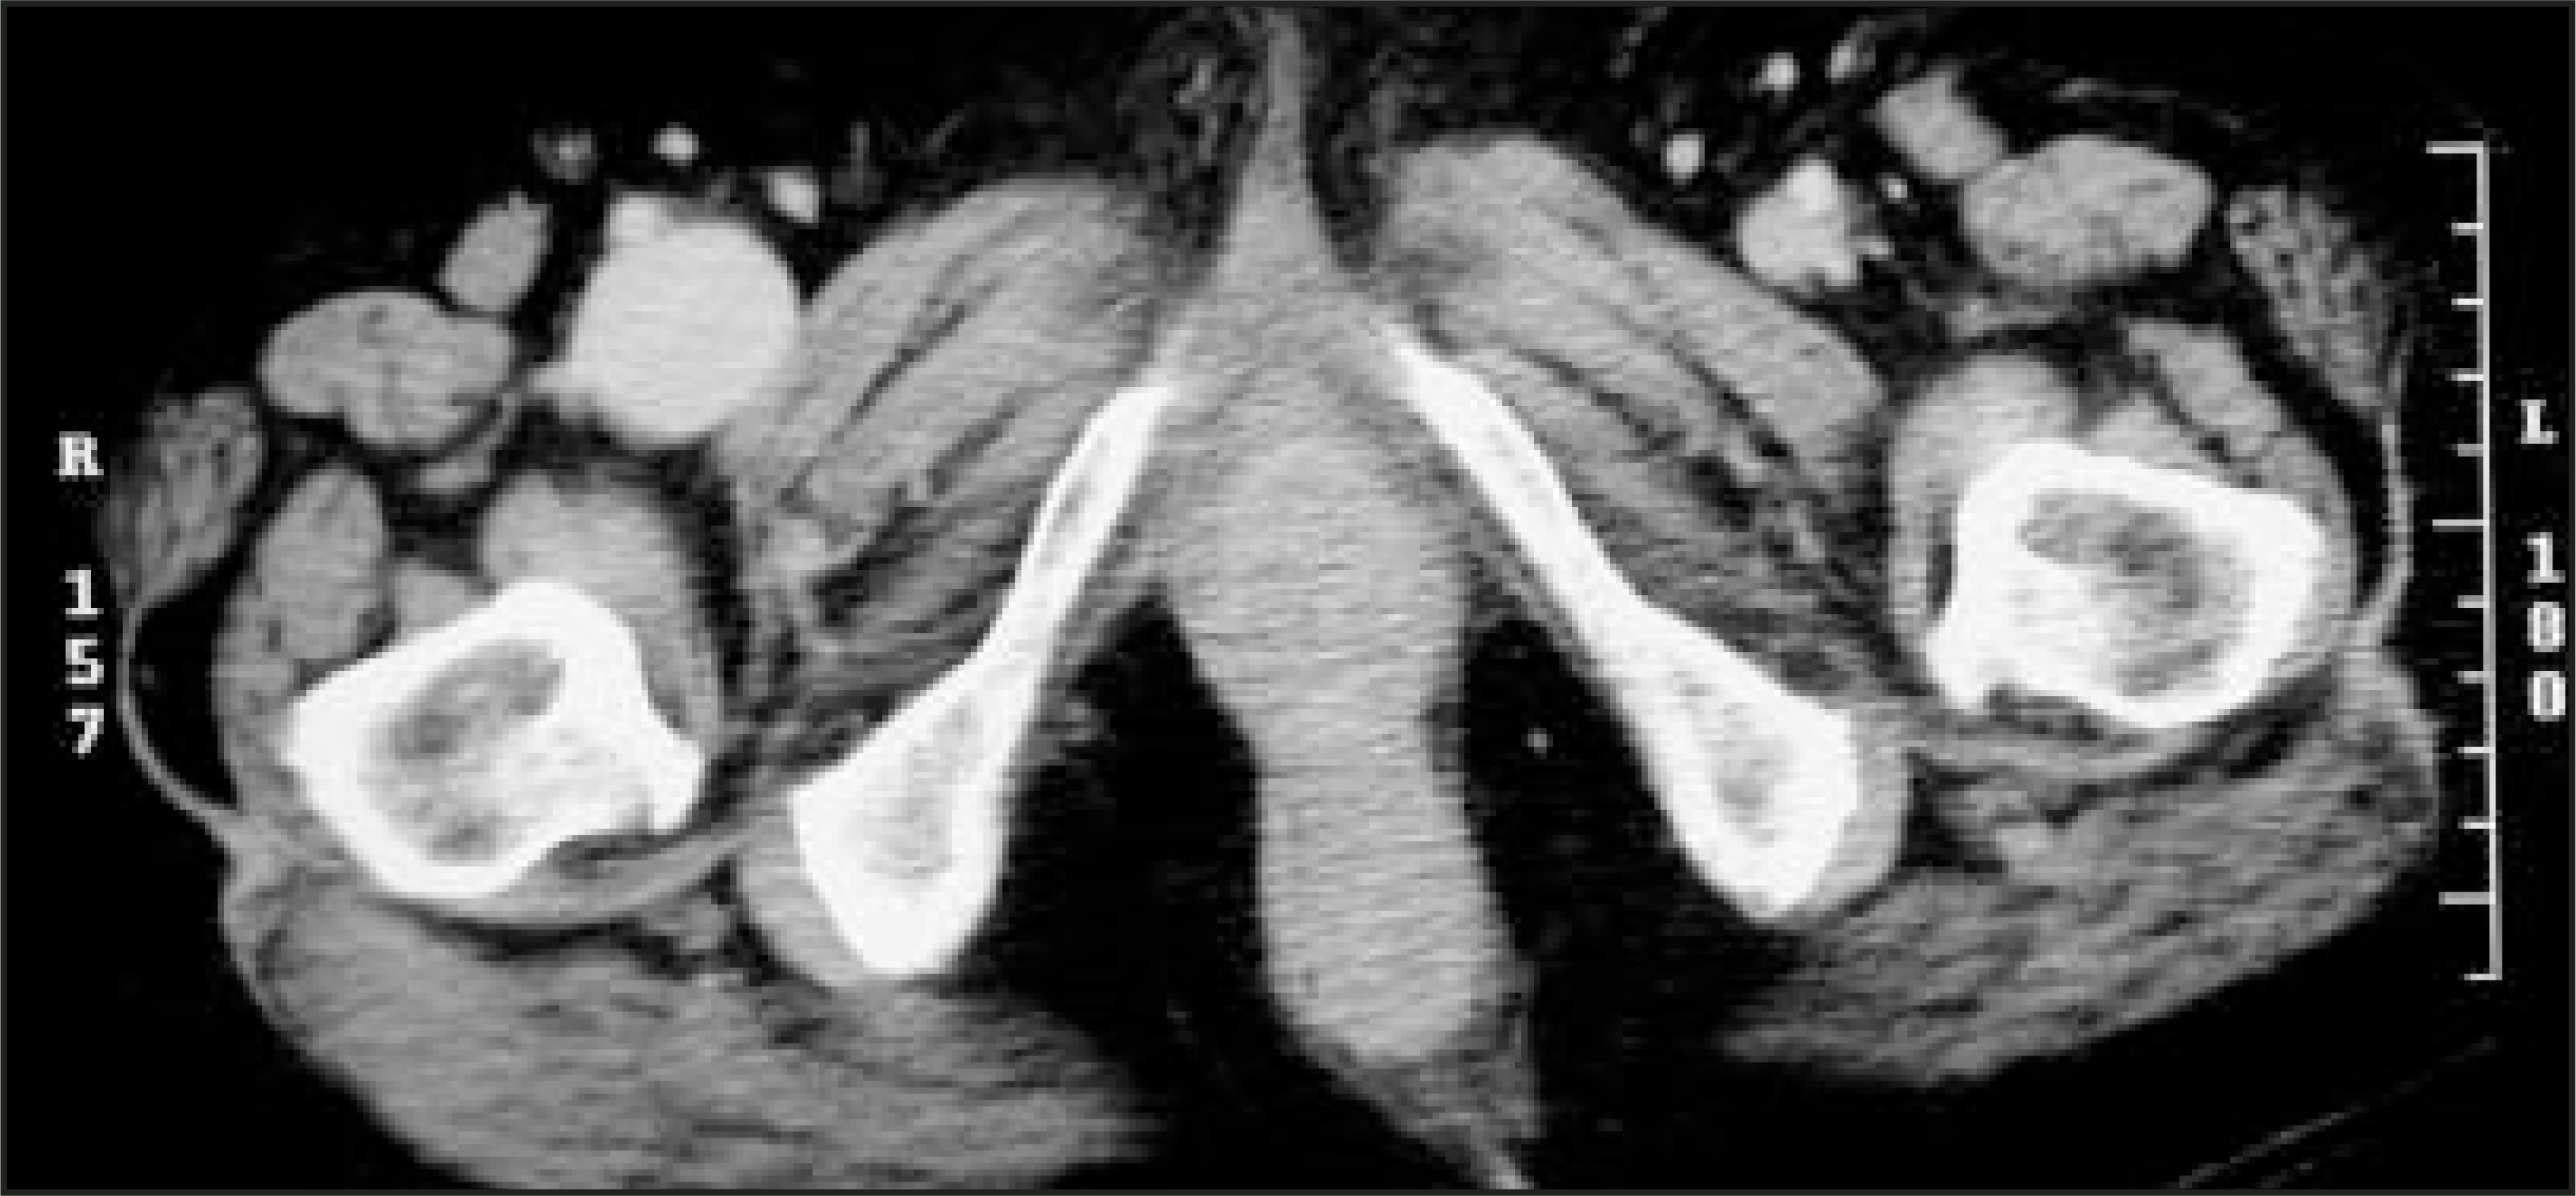
DIAGNOSIS
Iatrogenic arteriovenous fistula (AVF)
IMAGING FINDINGS
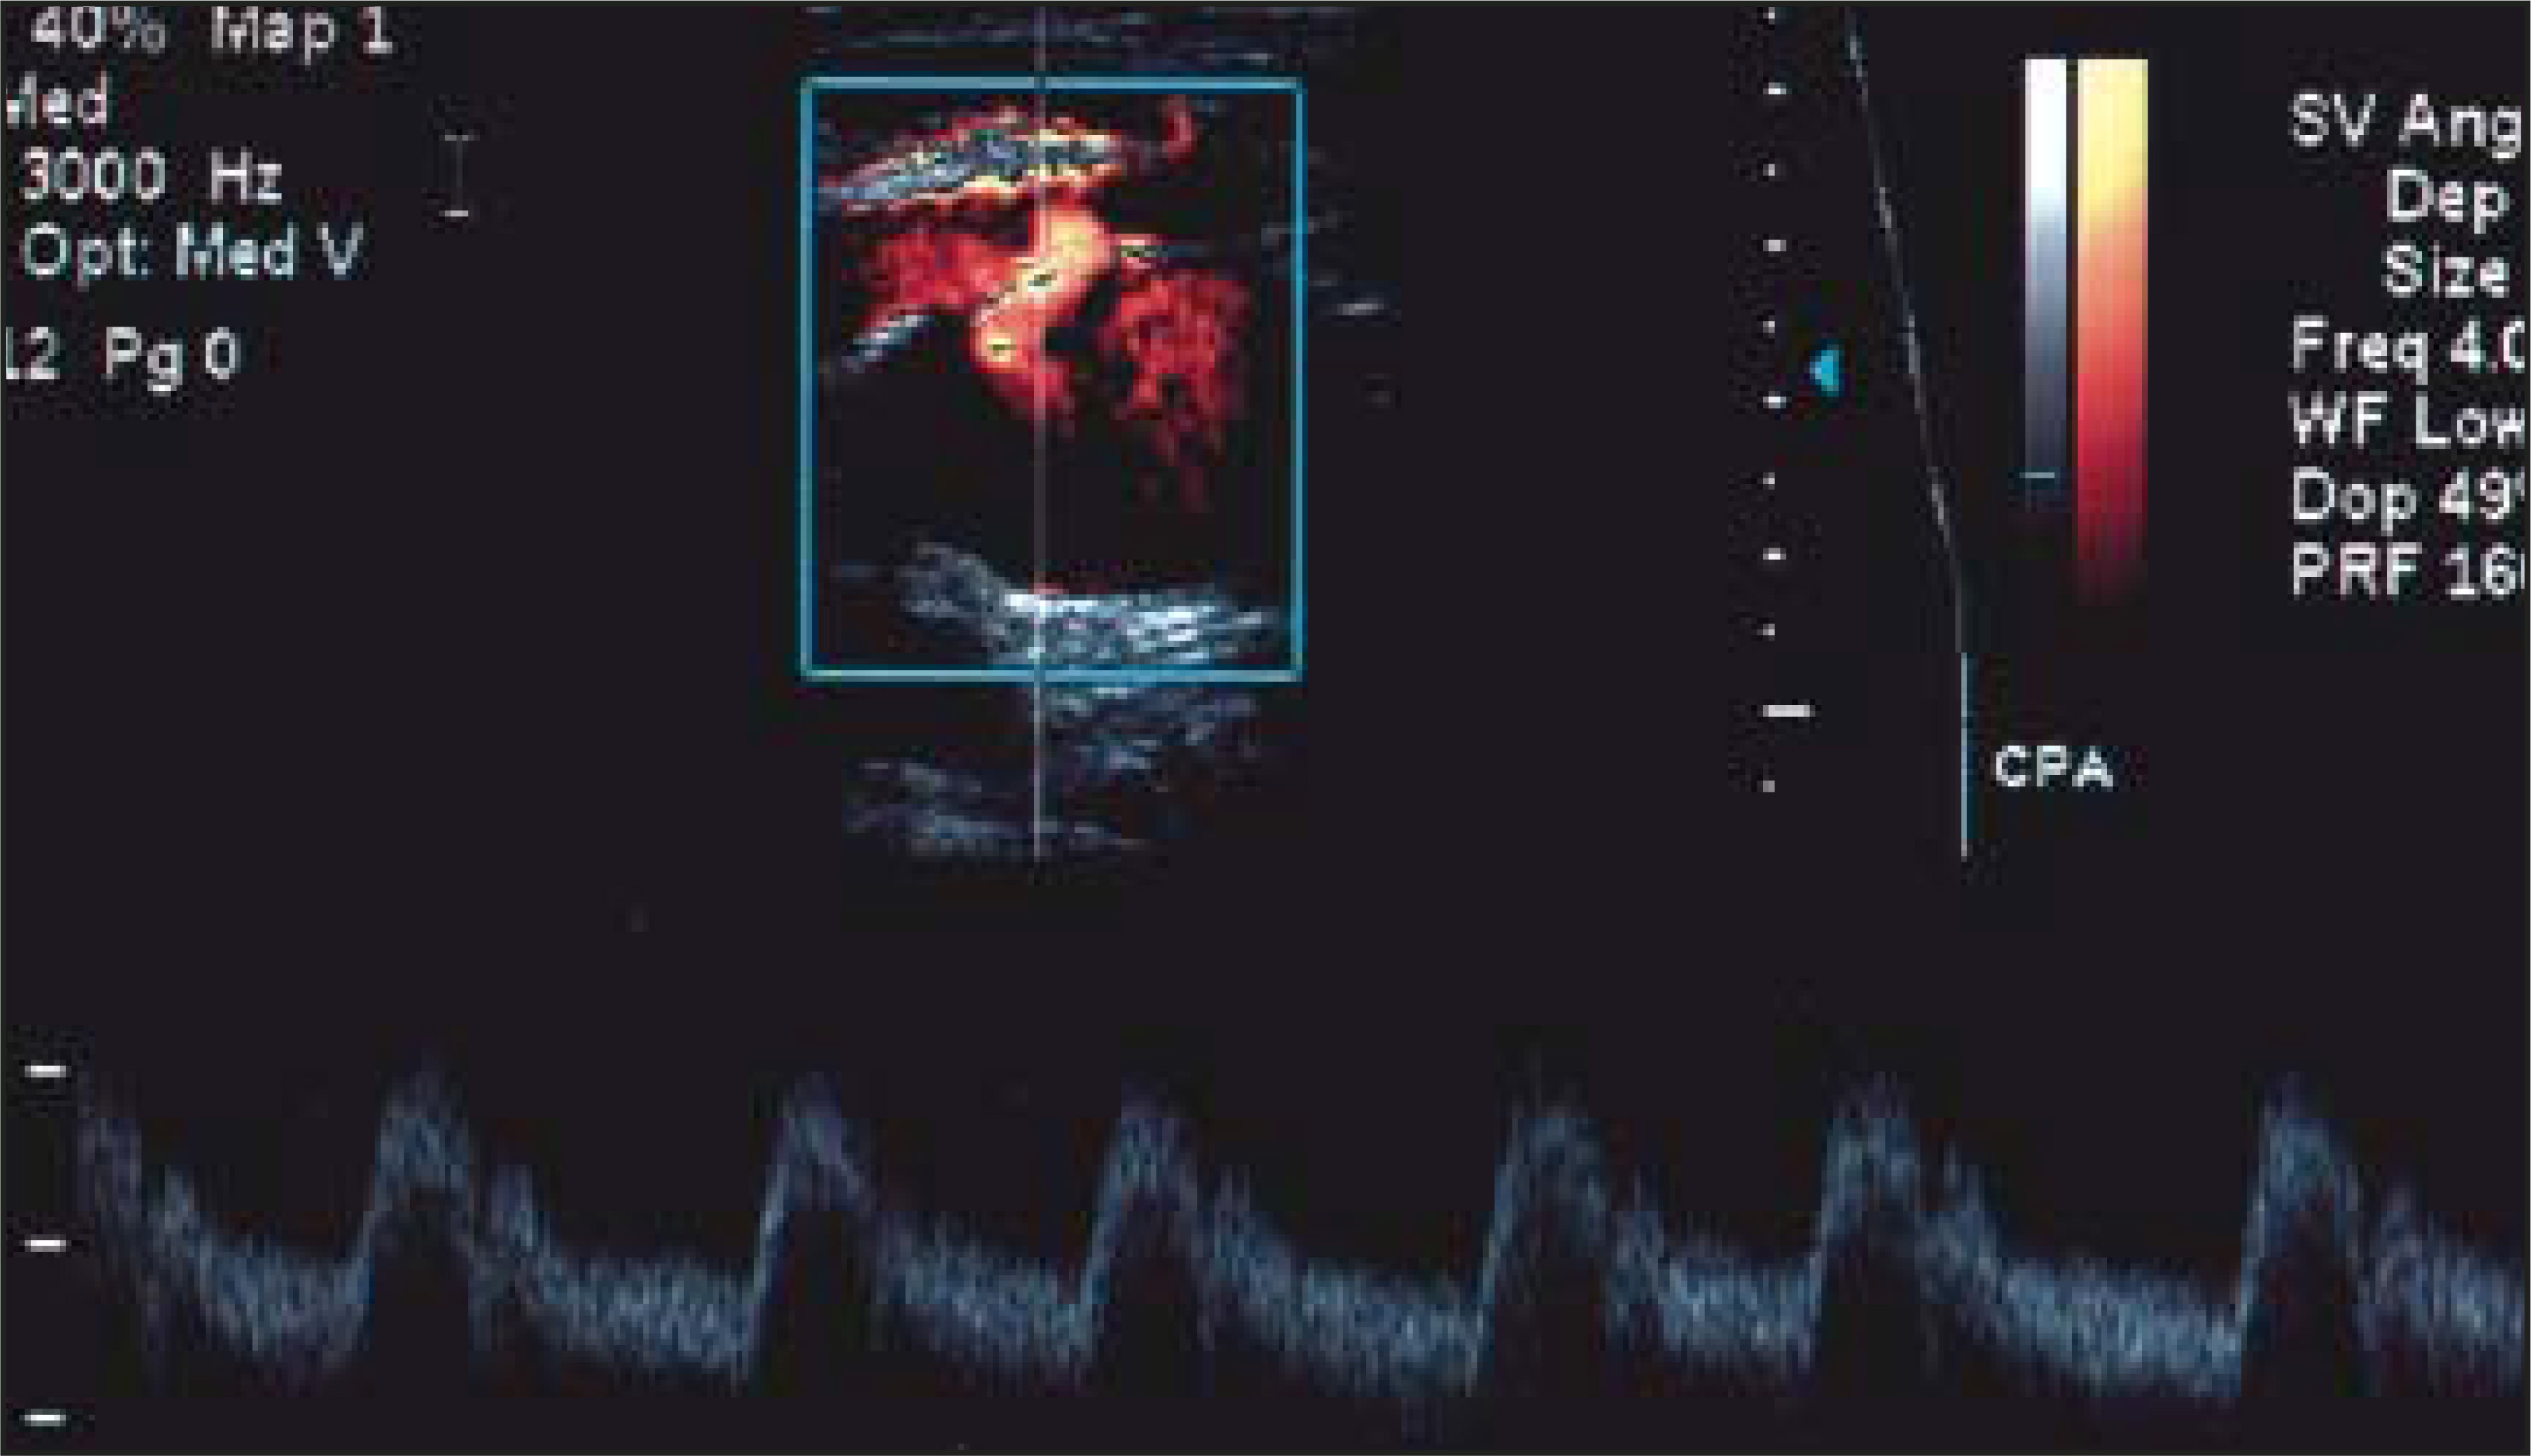
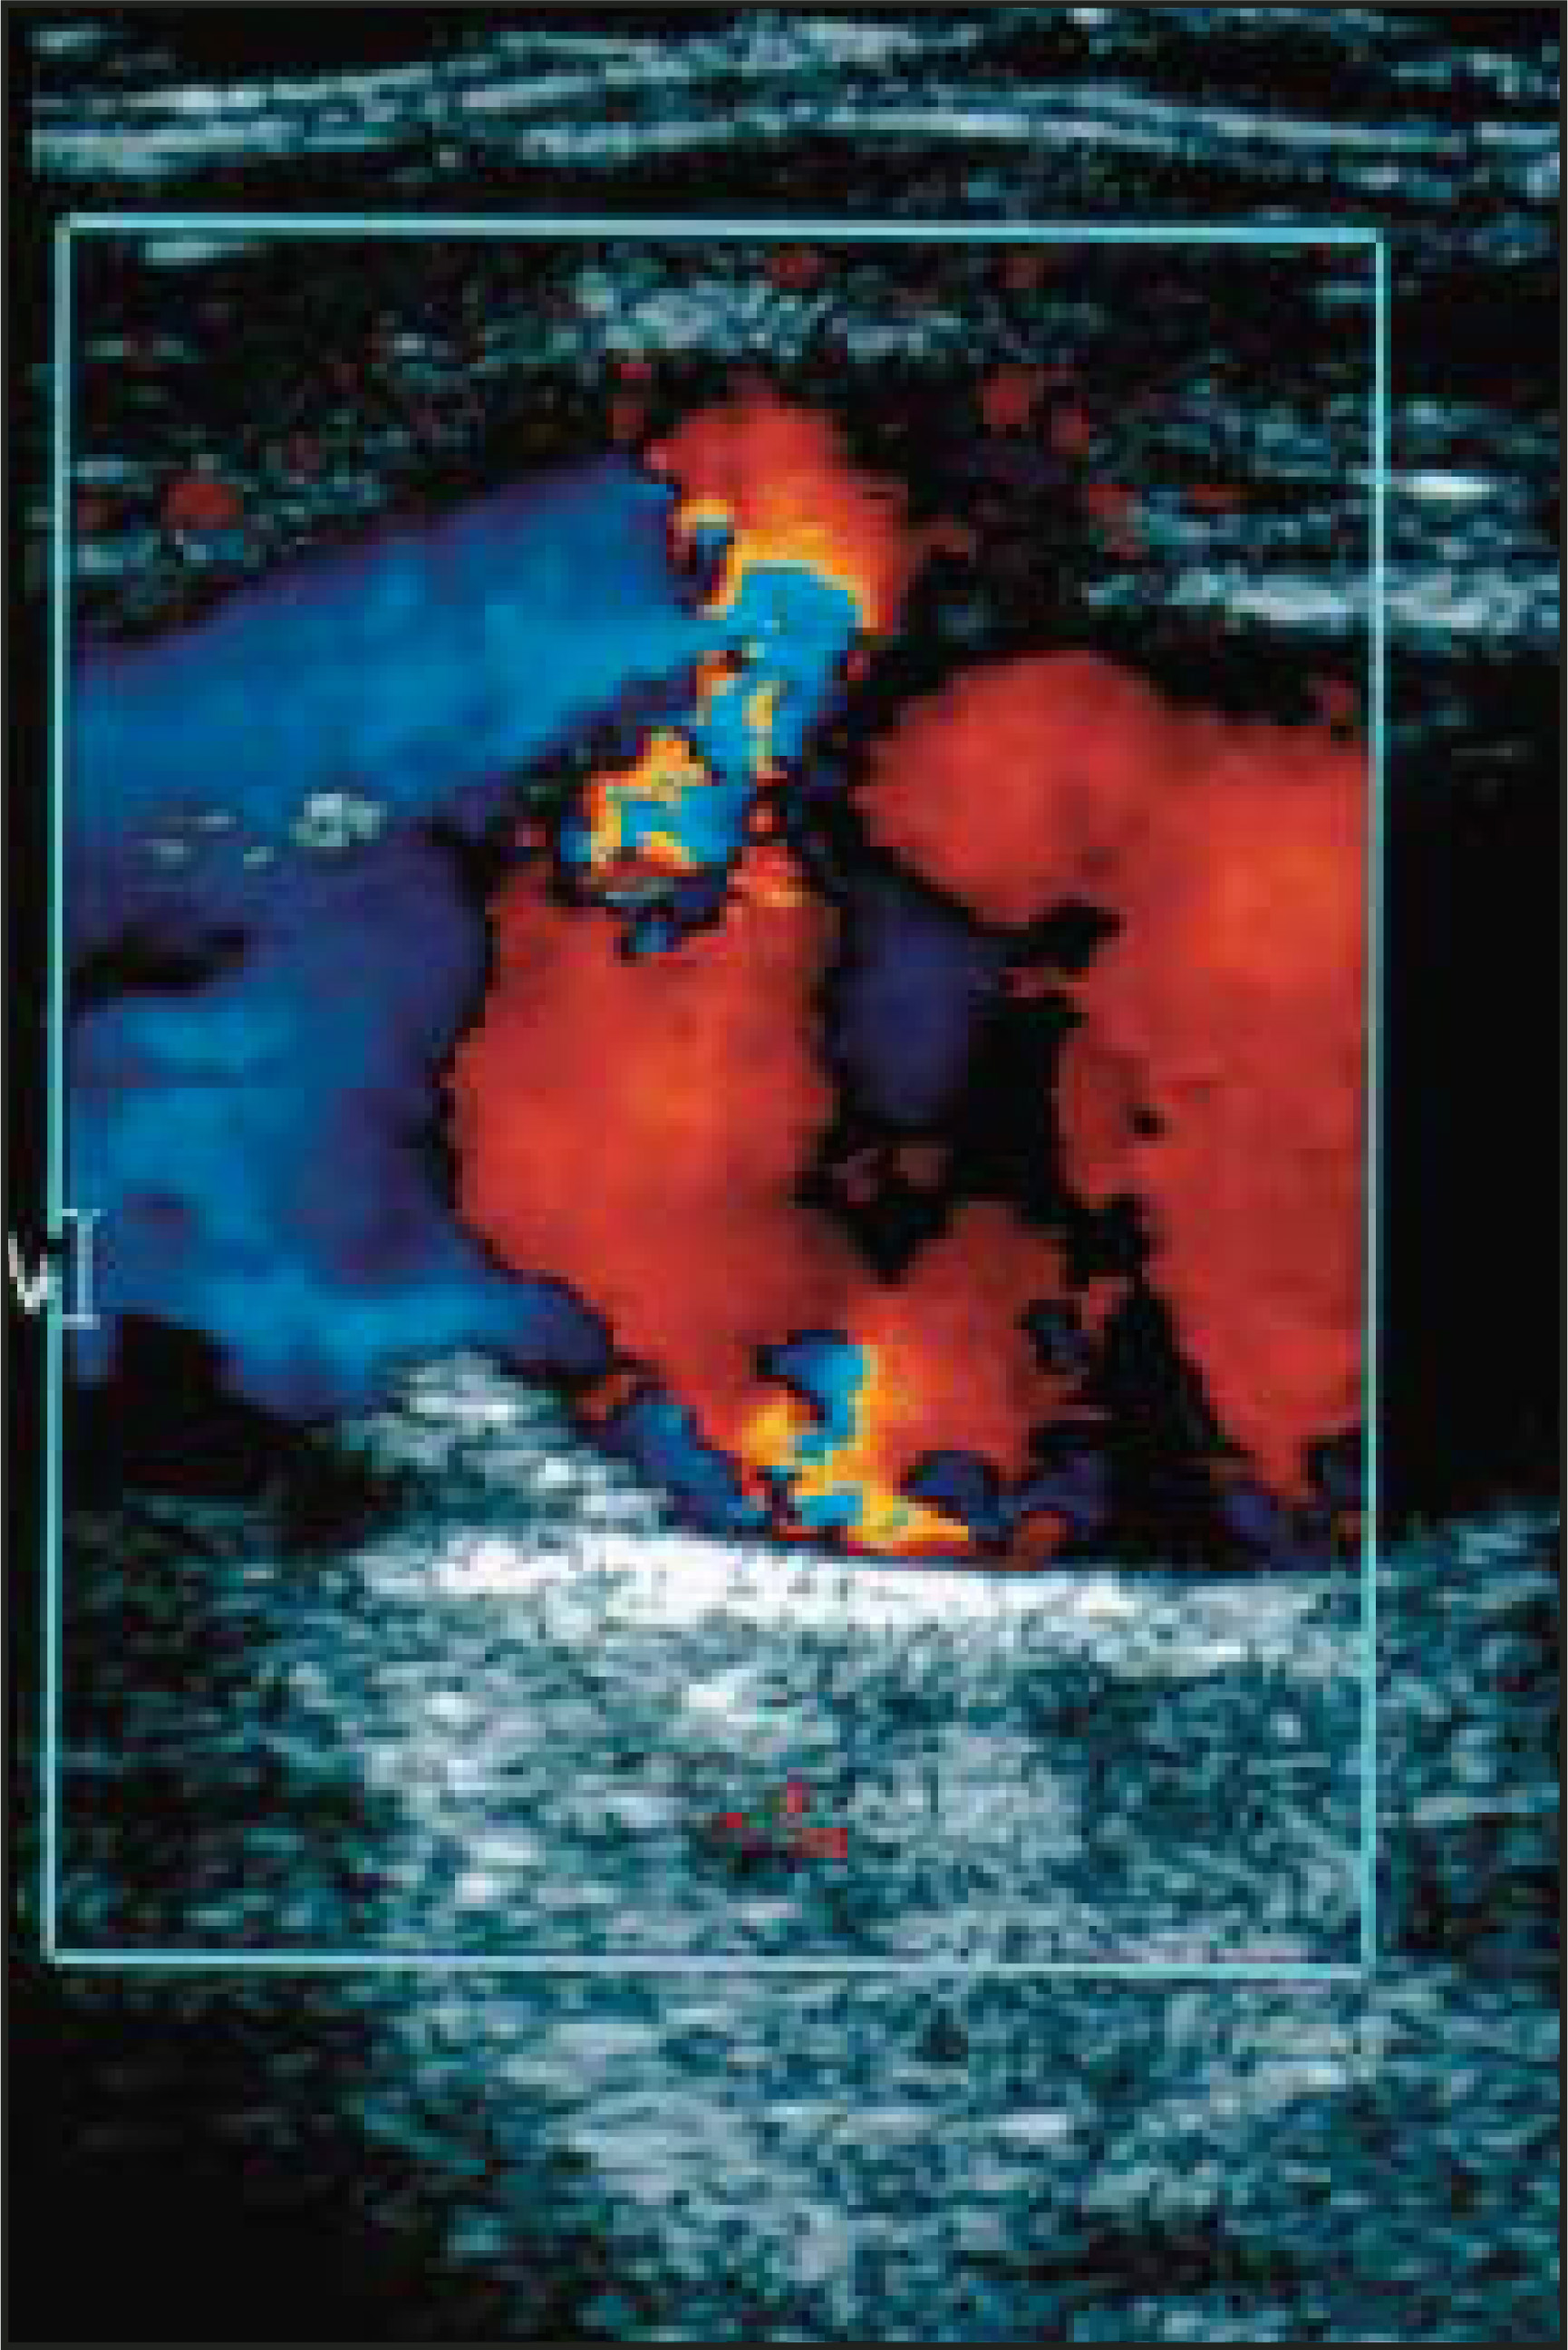
While the initial CT scan would strongly favor ateriovenous fistula (Figure 1), one could also consider a primary venous abnormality, such as Klippel-Trenaunay-Weber or an abnormally enlarged vein secondary to a more distal arteriovenous malformation. The ultrasound, however, allows the specific diagnosis of ateriovenous fistula to be made by the characteristic low-resistance waveform and visualization of the AVF (Figures 2 and 3). The iatrogenic nature is suggested by its location near the right common femoral artery and the history of prior cardiac catheterization.
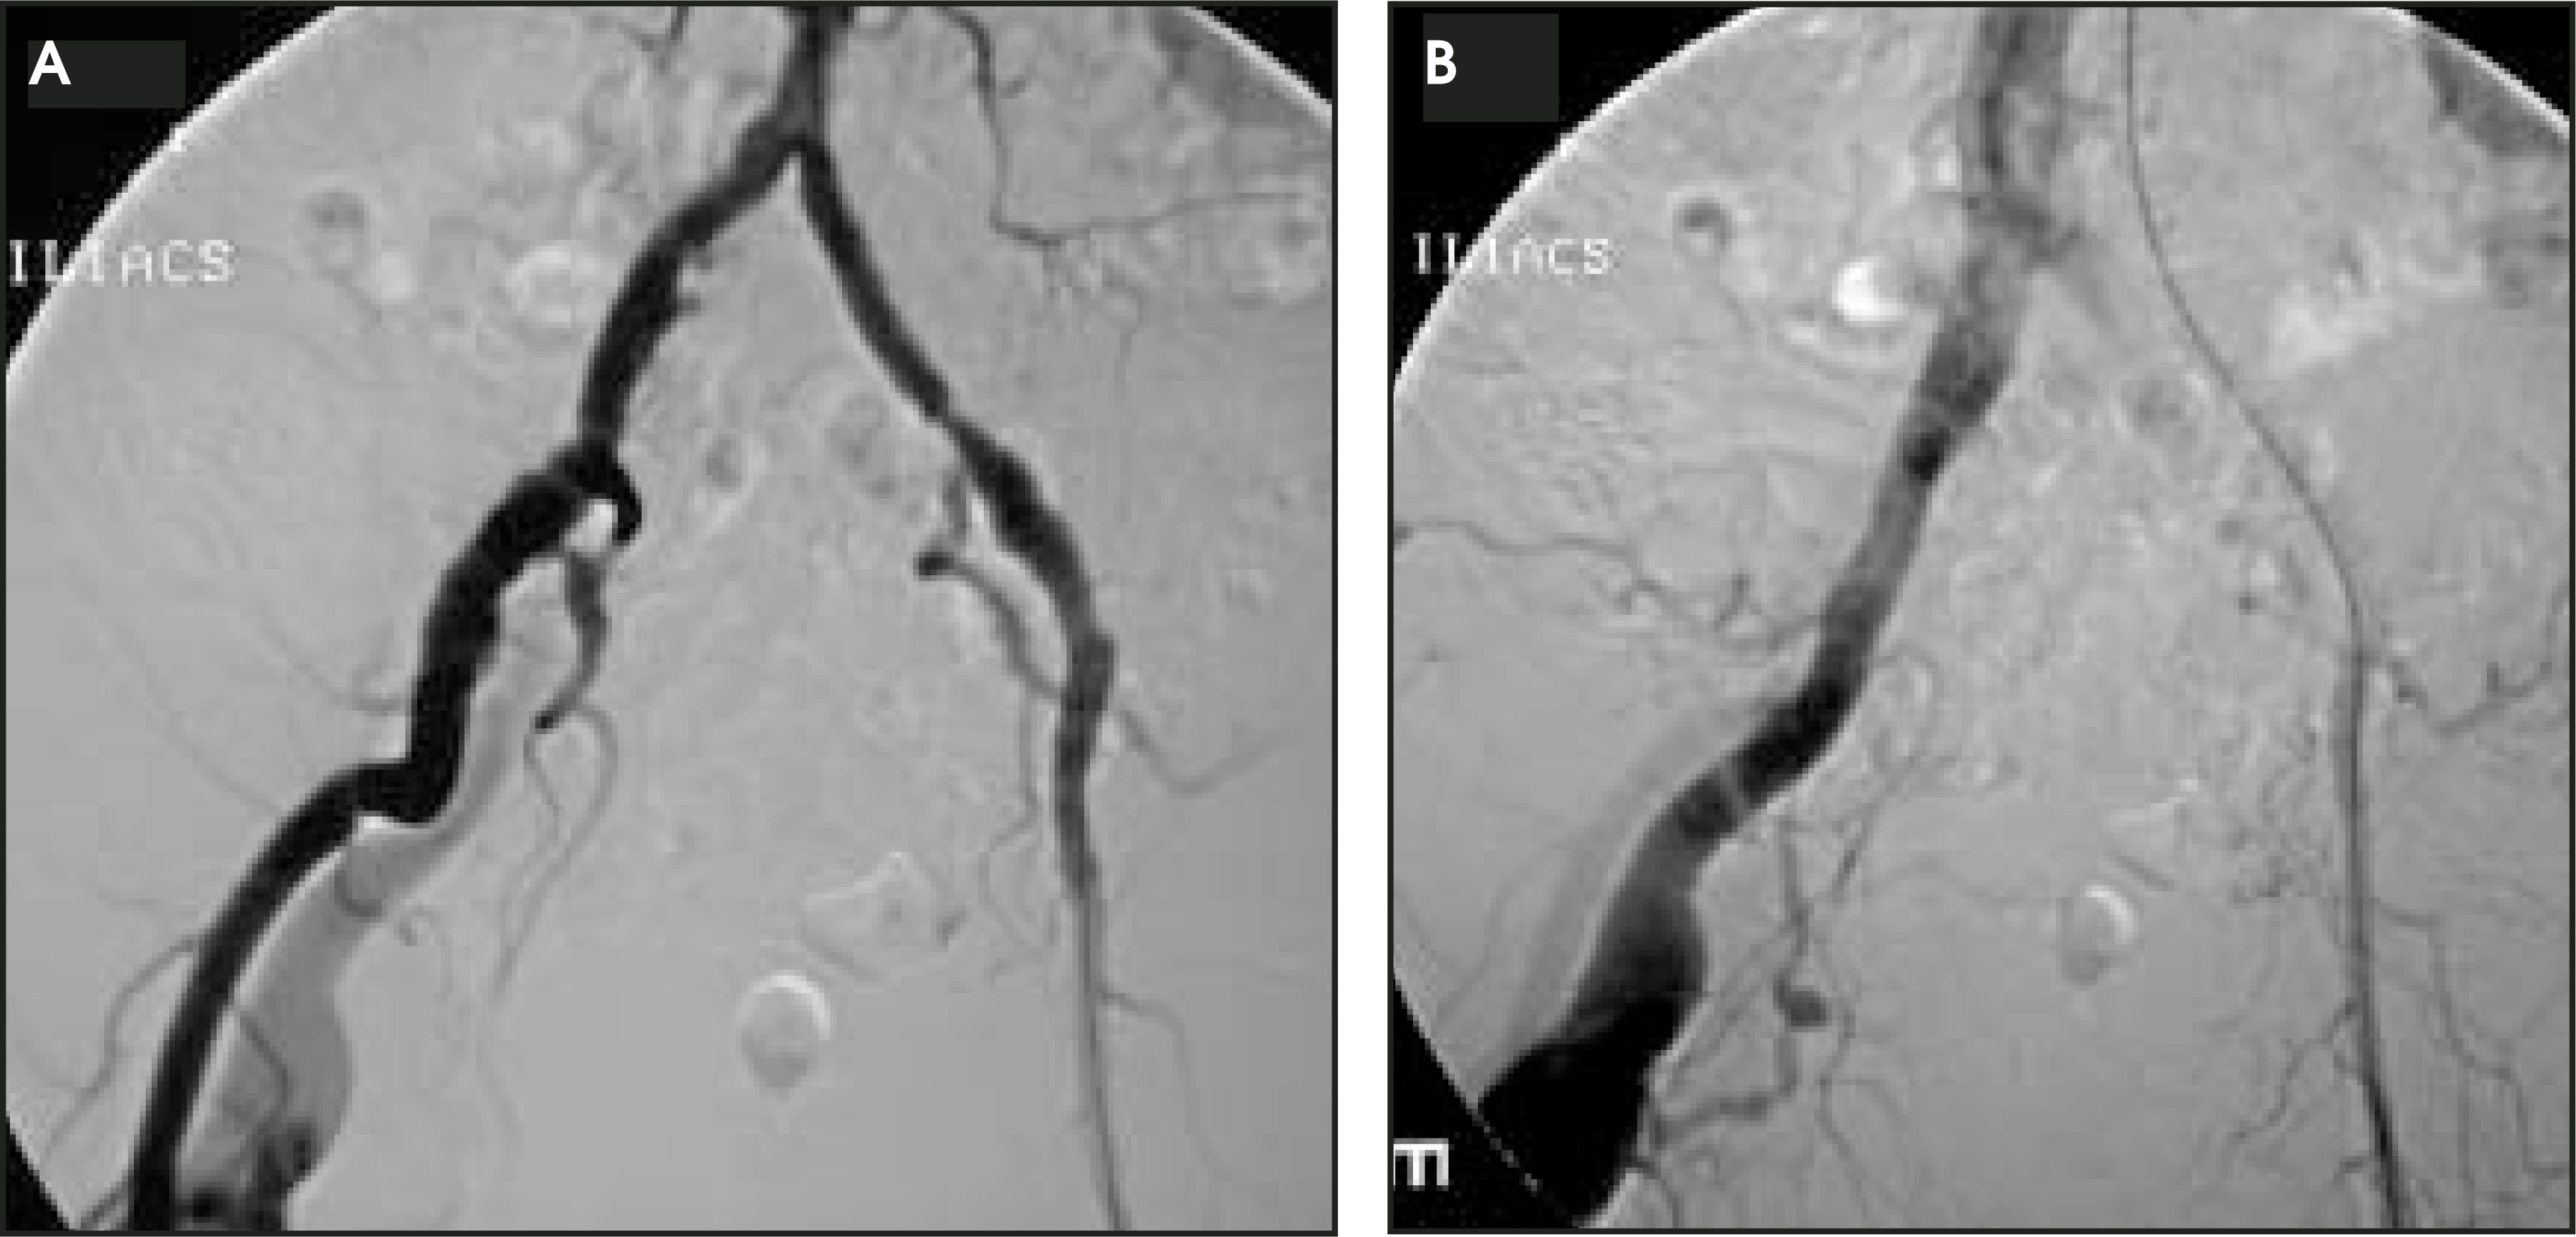
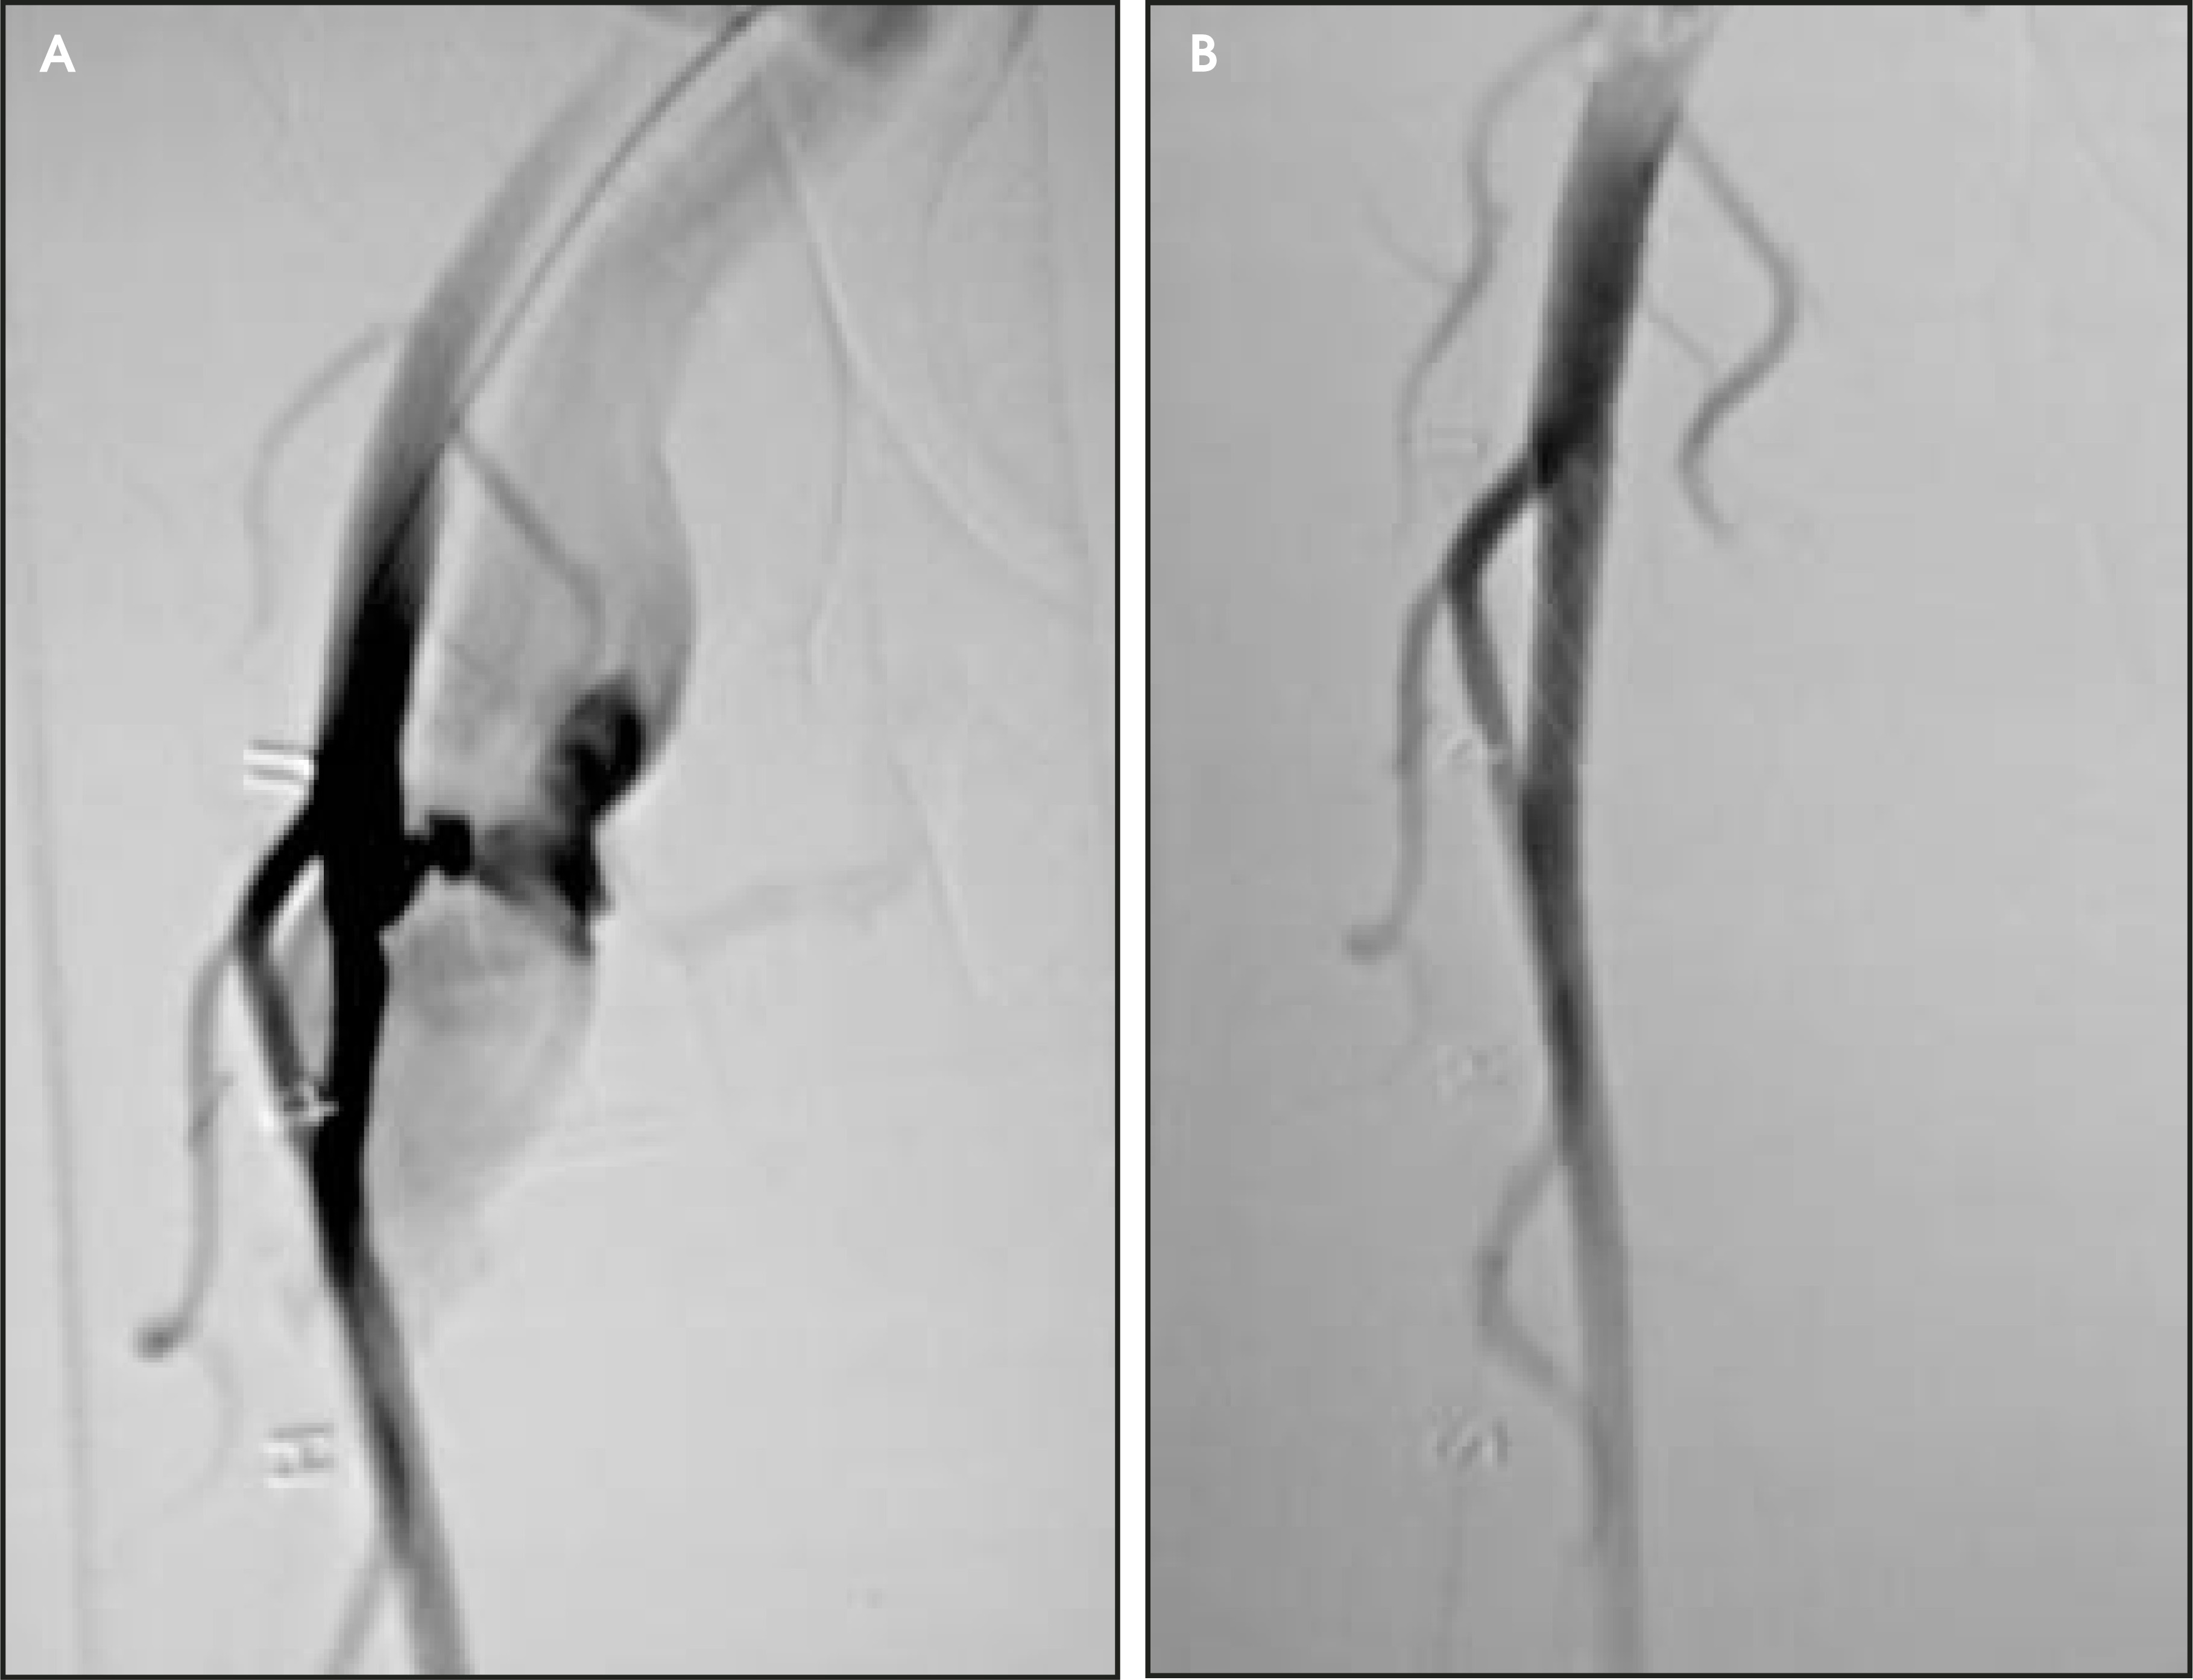
Conventional angiographic images during the arterial and venous phases showed rapid filling of the right superficial common femoral vein and external iliac system early in the arterial injection (Figure 4). A selective angiogram (Figure 5A) illustrated the actual fistula. Figure 5B presents the angiographic result after endovascular therapy with a covered stent.
DISCUSSION
Arterial venous fistula is an accepted complication of femoral access angiography. The incidence has been estimated at 0.02% to 0.9% after diagnostic angiography.1 Iatrogenic AVF is more often observed after utilization of large access sheaths and after procedures with difficult initial arterial access. Punctures below the common femoral artery are more likely to result in all groin complications, including fistula.2,3
The natural history of arterial venous fistula can be benign with spontaneous closure.5 However, other series suggest that spontaneous closure is more variable.6 Kresowik et al2 reported a prospective series on patients who underwent coronary angioplasty and found 4 cases of AVF in 144 patients (3.6% in this group). No fistula in this prospectively discovered group was seen to close spontaneously.2 Once identified, the lesions can either be followed with serial ultrasound,7 or an early attempt at ultrasound compression can be performed. As the fistula matures and widens, effective selective compression of the fistula may become difficult or impossible.
Indications for repair of AVF include: failure to spontaneously close within 2 months, arterial or venous enlargement, symptoms secondary to venous engorgement, congestive heart failure, and worsening of symptomatic claudication.10 In the patient reported here, her heart failure may have been aggravated by the shunt, and bilateral lower extremity claudication was present.
In this poor surgical candidate, a minimally invasive procedure was selected. The Wallgraft endoprosthesis (Boston Scientific, Watertown, MA) was utilized from an endoarterial approach. The stent was deployed and dilated with an 8-mm balloon from contralateral access. After balloon dilatation, the previously palpable groin thrill ceased. After the procedure, the patient was maintained on 325 mg of aspirin per day as an antiplatelet agent.
The Wallgraft endoprosthesis is a polyethelene-covered self-expanding stent, which is approved by the U.S. Food and Drug Administration for use in the trachea and bronchus. The Wallgraft has been used “off label” to exclude AVF, pseudoaneurysms, and aneurysms.
Several authors have reported their experiences with similar strategies of endovascular repair of iatrogenic or traumatic ateriovenous fistula.4,8,11-14 Thalhammer et al4 reported a series of successful closure of 26 of 29 fistulas or aneurysms using this technique with the Cragg-endoprosthesis,2 achieving closure in all cases and 83% patency at 1-year follow-up. Reubben and colleagues8 reported a series of 14 groin fistulas closed with stentgrafts.
Relative contraindications to an endoluminal covered stent strategy for the management of fistula include: fistula at bifurcation, renal failure, contrast allergy, and lesions over mobile joints. Absolute contraindications currently include: bacteremia, untreated infection, or an allergy to a stentgraft component. The Wallgraft has been shown (in sheep) to result in more intimal hyperplasia than its noncovered counterpart, the Wallstent.14
CONCLUSION
Small published series and anecdotal experience suggest that endovascular stent-graft therapy is a safe and effective alternative to surgery for 4,8,11-13 Given the increasing number of complex catheterization procedures being performed for cardiac, peripheral, and neurovascular indications, it is likely that the number of iatrogenic fistulas will increase.
References
- Spies J. Complications of diagnostic arteriography. Semin Intervent Radiol. 1994;11:93-101.
- Kresowik T, Khoury M, Miller B. A prospective study of the incidence and natural history of femoral vascular complications after percutaneous transluminal coronary angioplasty. J Vasc Surg. 1991;13:328-333.
- Altin R, Flicker S, Nadich H. Pseudoaneurysm and arteriovenous fistula after femoral artery catheterization: Association with low femoral punctures. AJR Am J Roentgenol. 1989;152:629-631.
- Thalhammer C, Kirchherr A, Uhlich F. Postcatheterization pseudoaneurysms and arteriovenous fistulas: Repair with percutaneous implantation of endovascular covered stents. Radiology. 2000;214:127-131.
- Kent K, McArdle C, Kenedy B. A prospective study of the clinical outcome of femoral pseudoaneurysms and arteriovenous fistulas induced by arterial puncture. J Vasc Surg. 1993;17:125-131.
- Hoffer E, Sclafani S, Herskowitz M, Scalea T. Natural History of arterial injuries diagnosed with arteriography. J Vasc Interv Radiol. 1997;8((1 Pt 1)):43-53.
- Igidbashian V, Mitchell D, Middleton W. Iatrogenic femoral artervenous fistulas: Diagnosis with color Doppler imaging. Radiology. 1989;170:749-752.
- Ruebben A, Tettoni S, Rossato D. Arteriovenous fistulas induced by femoral arterial catherization: Percutaneous treatment. Radiology. 1998;209:729-734.
- Andrews R, Venbrux A, Magee C, Bova D. Placement of a Flexible endovascular stent across the femoral joint: An in vivo study in the swine model. J Vasc Interv Radiol. 1999;10:1219-1228.
- Marin M, Veith F, Panetta T. Percutaneous transfemoral insertion of a stented graft to repair a traumatic femoral arteriovenous fistula. J Vasc Surg. 1993;18:299-302.
- Hilfiker P, Mahmood K, Kee S. Stent graft therapy for subclavian artery aneurysms and fistulas: Single-center midterm results. J Vasc Interv Radiol. 2000;11:578-584.
- Quinn S, Sheley R, Seonsen K. Endovascular stents covered with PTFE for the treatment of iliac artery aneurysms and fistulas. J Vasc Interv Radiol. 1997;8:1057-1063.
- Parodi J. Endovascular repair of abdominal aortic aneurysms and other arterial lesions. J Vasc Surg. 1995;21:549-557.
- Cejna M, Virmani R, Jones R. Biocompatibility and performance of the Wallstent and the Wallgraft, Jostent, and Hemobahn stent-grafts in a sheep model. J Vasc Interv Radiol. 2002;13:823-830.
Citation
. RCOM RADIOLOGICAL CASE OF THE MONTH. Applied Radiology. 2004;33(11):69-73. doi:10.37549/AR1295.